
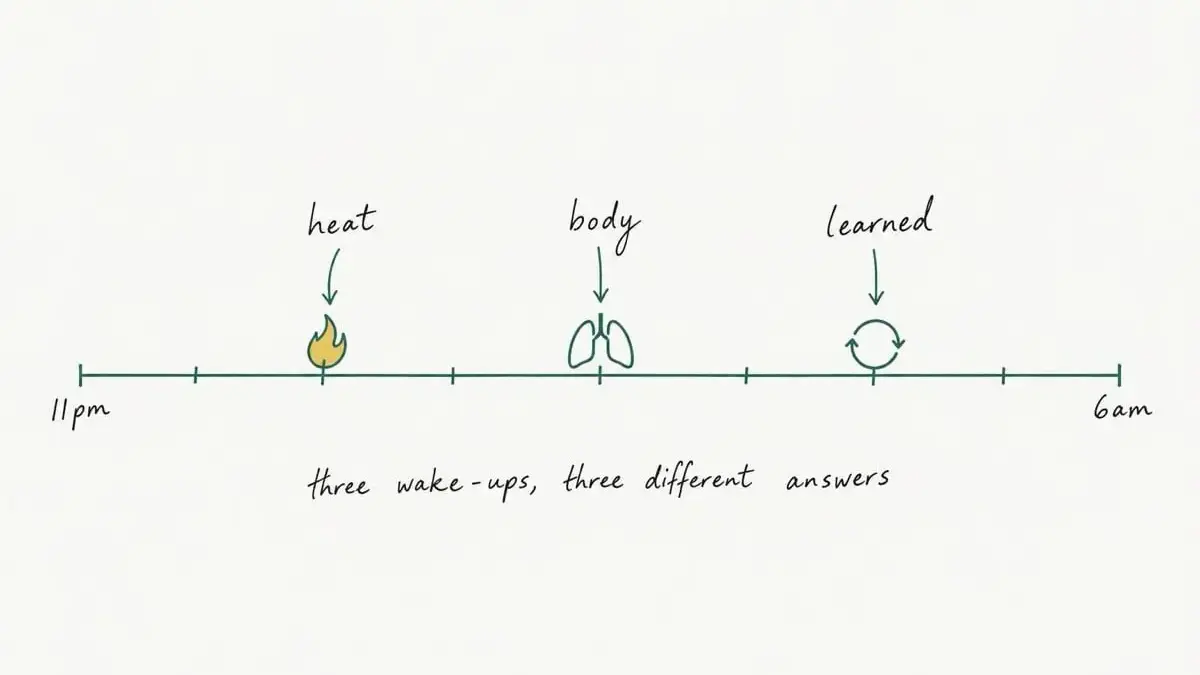
For millions of women entering midlife, the disruption of rest does not arrive as an occasional bout of restlessness or the simple fatigue of a stressful week. Instead, it manifests with a distinctive and exhausting rhythm: the difficulty of falling asleep compounded by the frustration of staying asleep. According to findings from the landmark Study of Women’s Health Across the Nation (SWAN)—a comprehensive research effort that followed 3,045 women enrolled between the ages of 42 and 52—the statistical odds of experiencing both types of sleep trouble escalate steadily across the menopausal transition.
The nights begin to repeat themselves with an unsettling uniformity. Nothing else in a woman’s professional or personal life has fundamentally changed, yet the architecture of her night has collapsed. This particular combination serves as the defining hallmark of midlife sleep disruption, and it explains precisely why generic, one-size-fits-all sleep advice routinely fails to help.
For a large proportion of women, the second half of the equation—staying asleep—is the loudest and most disruptive part. The pattern assumes a familiar, punishing shape. A woman might fall asleep by eleven o’clock without excessive difficulty, only to jolt awake at 2:40 a.m., feeling damp, kicking off the bedcovers, and then moments later pulling them back up as a chill sets in. She may drift off again, only to wake once more at 4:15 a.m., before finally resigning herself to get up at six because employment and daily responsibilities demand it.
By Thursday, the accumulated deficit takes its toll. A woman finds herself uncharacteristically short-tempered with the people she loves most and forced to reread the same professional email four times just to grasp its meaning. Secondary analyses spanning ten years of data from the same SWAN cohort revealed that self-reported insomnia symptoms affected 31 percent of women in early perimenopause during their first year, climbing to 39 percent by the tenth year. Among women in late perimenopause, the prevalence started at 32 percent and rose steeply to 48 percent.
These figures capture self-reported symptoms occurring at least three times a week rather than clinically diagnosed chronic insomnia, and they naturally fluctuate across different stages and years. Even so, the sheer scale of these numbers offers a vital reassurance: at 3 a.m., a struggling woman is not the isolated outlier she feels like. Yet perhaps the most insidious development is the emerging dread of the bed itself—a psychological shift that carries far more weight than any supplement bottle sitting on a kitchen counter.
Why the Usual Natural Remedies Keep Failing You
Natural remedies for broken midlife sleep typically fail because they are delivered as an undifferentiated list of options, completely lacking an internal hierarchy, clear mechanisms of action, or any rigorous grading of the underlying evidence. Melatonin stands as the clearest example of this disconnect. When pooled across four randomized clinical trials involving menopausal women, its measurable effect on overall sleep quality failed to reach statistical significance. In scientific terms, this indicates uncertainty rather than outright disproving, but that nuance rarely makes it onto the label of a retail box.
Herbal alternatives like valerian fare no better under scrutiny. An umbrella review published in 2024 synthesized eight systematic reviews examining valerian for sleep disturbances and concluded that the available evidence was weak or inconclusive, demonstrating no proven efficacy for insomnia.
Faced with these options, a woman typically selects a remedy, gives it a fair trial of two weeks, feels no perceptible difference, and quietly concludes that the failure lies within her own biology. In reality, the problem is not personal failure; it is structural. Patients are handed a crowded retail shelf and told to guess, which represents a profoundly flawed approach to treating menopause insomnia—a complex medical phenomenon driven by at least three distinct underlying causes.
Menopause Sleep Problems Are a Wake-Up Pattern, Not One Problem
Menopause-related sleep difficulties are not a single uniform problem, but rather at least three separate wake-up patterns wearing the disguise of a single symptom: heat-driven waking, body-driven waking caused by physiological events like disordered breathing, and learned waking that persists long after the initial vasomotor flashes have subsided. A remedy specifically aimed at one of these patterns does little to resolve the other two. Determining which pattern dominates a woman’s nights is what transforms a random list of tips into a coherent clinical decision.
Heat-driven waking is the phenomenon everyone pictures, and its physiological reality is well-documented. In a study of 168 midlife women monitored using actigraphy, 78 percent of objectively recorded nocturnal hot flashes coincided with an awakening episode. Furthermore, women were significantly more likely to be awake in the five minutes immediately following a flash than in the minutes leading up to it. While mere concurrence does not prove that every single awakening originates with a flash, the statistical link is difficult to dismiss.
Body-driven waking represents the pattern most frequently missed by primary care providers. Data from the Sleep in Midlife Women Study demonstrated that the adjusted apnea-hypopnea index was approximately 31 percent higher after the menopausal transition than before it. This metric measures breathing events rather than counting new clinical apnea diagnoses, but its presentation is crucial: women with obstructive sleep apnea often present to their doctors reporting insomnia, fatigue, and low mood rather than the stereotypical loud snoring, which remains a primary reason the condition goes widely undiagnosed in women.
Learned waking explains why many women remain wide awake at 3 a.m. years after their hot flashes have completely faded. Over time, the bed has transformed from a place of rest into an arena where they lie awake performing mental arithmetic about the demands of the following day. This is no longer primarily a hormonal disruption; it is a conditioned behavioral pattern, and it happens to be the specific wake-up pattern backed by the strongest non-pharmacological treatments available.
While sorting nights into these distinct categories serves as a conceptual framework rather than a rigid clinical classification—and real-world weeks frequently blend them—the categorization remains immensely useful. Each group points directly toward a different next step.
Natural Remedies, Ranked by the Evidence Behind Them
When evaluated strictly by the strength of the scientific evidence supporting them, natural remedies for menopause sleep problems fall into a clear hierarchy: cognitive behavioral therapy for insomnia ranks first, regular exercise places second, and nutritional or herbal supplements occupy a distant third. In a randomized controlled trial involving 106 midlife women suffering from frequent hot flashes and insomnia, telephone-delivered cognitive behavioral therapy for insomnia improved insomnia severity scores by roughly 5.2 points more than a menopause-education control group at eight weeks, with those gains successfully maintained at the 24-week mark. No dietary supplement possesses clinical evidence in that range.
This ranking reflects the hierarchy of scientific data rather than personal preference, and the evidence supporting each tier varies dramatically in robustness.
First: CBT-I, Which Is a Treatment, Not a Tip
Cognitive behavioral therapy for insomnia is a short, structured course of behavioral modification—typically lasting between four and eight sessions—delivered either by a trained clinician, a specialized therapist, or a guided digital program. It targets the fundamental mechanics of sleep: establishing a single, unyielding wake time every day, restricting time spent in bed to match the actual amount of sleep a person is currently achieving, getting out of bed instead of lying awake, and actively dismantling the late-night thought loops that perpetuate insomnia.

This approach aligns precisely with professional clinical guidance. The American College of Physicians recommends cognitive behavioral therapy for insomnia as the initial, first-line treatment for all adults suffering from chronic insomnia, issuing a strong recommendation based on moderate-quality evidence, with pharmacological interventions reserved for shared decision-making if behavioral therapy alone proves insufficient. While that guideline applies broadly to adults with chronic insomnia rather than exclusively to menopausal populations, the clinical trial cited earlier provides the direct bridge: its participants were specifically midlife women dealing with frequent hot flashes alongside insomnia.
One critical distinction warrants attention. The American Academy of Sleep Medicine strongly recommends the full, multi-component version of cognitive behavioral therapy for insomnia while explicitly advising against relying on generic sleep hygiene tips as a stand-alone therapy. Consequently, the familiar, tidy list of habits—keeping the room dark, eliminating screens, and avoiding late caffeine—represents merely the foundational floor of treatment, not the treatment itself.
Second: Exercise, With an Honest Effect Size
Pooled individual-participant data across four trials conducted by the Menopausal Strategies: Finding Lasting Answers for Symptoms and Health network found that structured exercise reduced Insomnia Severity Index scores by an average of 2.1 points relative to control groups, compared to the 5.2-point reduction achieved by cognitive behavioral therapy for insomnia. A two-point improvement represents a genuine, albeit modest, clinical benefit—worth pursuing, but insufficient to carry the entire therapeutic burden alone. Maintaining regular physical movement through a particularly exhausting month can prove challenging, which makes strategies focused on midlife habit consistency vital for long-term adherence.
Third: Supplements, With Their Evidence Attached
Evaluating dietary and herbal supplements requires a close look at the clinical data, which is frequently omitted from commercial marketing materials. Supplements interact continuously with prescription medications and with one another, making professional consultation with a clinician or pharmacist essential before introducing any new product.
A Note on the Cool-Bedroom Advice
Nearly every popular article addressing midlife sleep recommends lowering the ambient temperature of the bedroom, yet controlled clinical evidence specifically demonstrating that room temperature treats menopausal insomnia remains sparse. What research does show is the broader physiological scale of temperature regulation: in a controlled study involving healthy adults, artificially warming the skin of the torso and upper legs by less than one degree Celsius shortened sleep-onset latency by approximately three minutes. Because that study did not focus on menopause or ambient cooling, it neither definitively supports nor refutes standard bedroom advice.
The absence of robust clinical trials proving temperature regulation cures insomnia does not mean cooling is useless; keeping a fan running and choosing breathable bedding certainly mitigates the physical misery of night sweats. These measures should be viewed as practical comfort rather than curative treatment, and nobody should expect a lowered thermostat to resolve a ingrained 3 a.m. thought loop.
What One Week of This Actually Looks Like
In practice, addressing midlife sleep systematically is remarkably unglamorous. It begins with selecting a single wake time and holding it rigidly, including on weekends. Each morning involves recording three simple details: the approximate hour of waking, whether heat played a role, and whether any respiratory issues or daytime fatigue surfaced. The deliberate choice is made to stop accumulating random interventions. By the fifth day, the personal log—rather than a supplement label—reveals which specific wake-up pattern is dominating the night.
Consider two hypothetical readers illustrating the diverging paths of midlife sleep recovery. Tricia, aged 49 and in early perimenopause, maintains a log showing four awakenings across seven nights, three of which required changing damp sheets and turning on a fan, with no reported breathing issues. Her pattern is clearly heat-driven. Her action plan avoids purchasing eight different products; instead, she establishes a fixed wake time of 6:15 a.m., incorporates regular daily walks, adopts breathable bedding, and notes the frequency of her night sweats to share at her next medical appointment.
At the same time, Tricia’s daily log accomplishes something quieter and more valuable: it translates the subjective feeling of "I never sleep anymore" into precise, actionable clinical data: four nights out of seven, three involving night sweats, persisting for eleven weeks.
Marlene, aged 54 and two years past her final menstrual period, experiences virtually no hot flashes. Yet she consistently wakes at 3:10 a.m., with a log showing zero heat-related disruptions and a strong habit of lying in bed for 90 minutes mentally drafting tomorrow’s to-do list. Furthermore, her breathing column is not blank; her spouse has noted snoring on multiple occasions, and she frequently finds herself falling asleep in front of the television by 8 p.m. Her log generates two distinct clinical steps: discussing cognitive behavioral therapy for insomnia to address her learned behavioral waking, and raising the persistent snoring and daytime sleepiness during the same medical visit rather than dismissing them as ordinary fatigue. In the interim, she resolves to get out of bed after lying awake for 20 minutes, refusing to teach her brain that the bed is a place for cognitive labor.
Both women commit to maintaining their logs for a full week before altering any other variables. That single rule prevents the common trap of launching magnesium supplements, blackout curtains, specialized pillows, and sleep-tracking apps all in the same week, which ultimately obscures which intervention, if any, is working.
When This Needs a Clinician, Not a Remedy
Certain nocturnal symptoms transcend the scope of over-the-counter remedies and lifestyle adjustments. Loud snoring, breathing that repeatedly stops and starts, gasping or choking sounds during sleep, and persistent, profound daytime fatigue are identified by major health authorities as primary indicators of obstructive sleep apnea, warranting formal medical evaluation rather than experimentation in the supplement aisle. The same applies to sleep disturbances that persist at least three times a week for three months or longer—the established diagnostic threshold for chronic insomnia defined by the American Academy of Sleep Medicine.
Dismissing these symptoms with the assumption that "it’s just menopause" is the single factor most likely to cost a patient months or years of unnecessary suffering. The research linking midlife hormonal transitions to increased apnea indices highlights why this matters so deeply: insomnia, fatigue, and low mood are precisely the ways sleep-disordered breathing frequently presents in women.
Hormone therapy is a valuable topic to raise during such medical consultations, representing a clinical decision best made in partnership with a healthcare provider. Position statements from professional organizations like the North American Menopause Society identify hormone therapy as the most effective systemic treatment for moderate to severe hot flashes and night sweats, while noting concurrent improvements in sleep quality when sleep disruption is directly tied to those vasomotor symptoms. It is not designed to function as a stand-alone treatment for primary insomnia, and its suitability depends entirely on an individualized assessment of potential benefits and risks.
Start With One Night, Not Eight Changes
Selecting a consistent wake time before purchasing any remedy establishes the necessary foundation for recovery. Placing a simple notepad by the bedside to record the hour of waking, the presence of heat, and any observations regarding breathing or daytime fatigue for seven straight days provides an inexpensive diagnostic tool. This simple log replaces guesswork with data, transforming a confusing array of natural remedies into a targeted discussion for a clinician and offering a clear, evidence-based path forward out of midlife sleep disruption.


