
You finish a full workday, answer your teenager’s school message, pick up a prescription for your father, and call the insurance company from the grocery-store parking lot. At 9:40 p.m., someone tells you to make time for self-care. The advice is not wrong. It is just too small for the load.
Caregiving can spread quietly and relentlessly into work, sleep, money, marriage, parenting, and your own physical and mental health until no single task looks impossible, but the whole week does. You may still be handling every medical appointment and insurance bill with absolute precision, yet find yourself snapping at the person you love, forgetting routine daily details, or feeling numb and detached when another urgent request arrives.
This pervasive pattern deserves professional attention and systemic understanding, not a superficial character judgment. What is commonly referred to as caregiver burnout is, at its core, a useful descriptor for cumulative human depletion under sustained care demands. It is not a formal medical diagnosis you can definitively confirm from a quick online checklist, nor is it proof that you have stopped caring about your loved one.
For individuals facing immediate crises, such as thoughts of self-harm or harming someone else, an inability to keep yourself or the person in your care safe, or any other immediate emergency, local emergency services remain the vital first point of contact. In the United States, individuals can call or text 988 or utilize the 988 Suicide & Crisis Lifeline for immediate support.
What is caregiver burnout?
Caregiver burnout manifests as a profound pattern of physical, emotional, and mental depletion directly linked to sustained caregiving demands compounded by insufficient support, control, or recovery time. It frequently shows up as deep exhaustion, emotional detachment, irritability, a sense of dread regarding routine tasks, frequent mistakes, or a severely reduced ability to manage daily life. While the term describes a very real lived experience, it is not a standalone medical diagnosis. Similar symptoms can frequently stem from clinical depression, sleep disorders, medication side effects, or other underlying health problems that require comprehensive professional assessment.
A peer-reviewed framework for informal caregiving treats burnout as the result of multiple interacting conditions: the physical and emotional care setting, the specific resources available to the caregiver, the surrounding environment, how demands are appraised by the individual, and the unique dynamics of the relationship itself. Importantly, this research does not reduce a complex systemic problem to weak personal resilience.
Burnout research also operates with real clinical boundaries. A comprehensive review published in 2023 in the BMJ argued that, after decades of study, no universally valid clinical diagnosis for burnout has been firmly established. That clinical reality does not make the distress imaginary or insignificant. Rather, it means that a simple label should never replace a thorough professional evaluation when symptoms persist, worsen, or actively interfere with personal safety and daily functioning.
The sheer scale of the issue underscores its societal impact. According to estimates by AARP and the National Alliance for Caregiving, approximately 63 million US adults—nearly one in every four—provided ongoing care to an adult or child with a medical condition or disability. While this figure does not represent a direct caregiver-burnout rate, it vividly illustrates just how many households quietly carry massive amounts of labor that frequently remains invisible to the outside world.
Caregiver stress, burnout, and compassion fatigue are not interchangeable
It is crucial to distinguish between various forms of emotional and physical strain. Caregiver stress represents the immediate, acute pressure of daily care demands. Burnout, by contrast, describes a cumulative depletion that occurs when those high demands continue over time without adequate resources or recovery periods. Compassion fatigue and secondary traumatic stress focus more specifically on the psychological impact of repeated exposure to another person’s suffering, while clinical depression is a distinct medical condition rather than merely a stronger word for burnout. Although these experiences frequently overlap in daily life, researchers have yet to draw clean clinical borders that allow a simple checklist to sort them safely.
Research conducted among medical professionals has revealed significant overlap among burnout, compassion fatigue, and secondary traumatic stress, alongside unresolved boundaries between burnout and depression. Because that particular sample consisted of professionals rather than unpaid family caregivers, the findings do not transfer perfectly to every domestic situation. Therefore, understanding caregiver burnout in practice means using these conceptual distinctions for general direction rather than definitive self-diagnosis.
Individuals do not need the perfect clinical label before reaching out for help. If low mood, persistent hopelessness, panic attacks, severe sleep disruption, chronic pain, increased substance use, or a general difficulty functioning persists or worsens, contacting a qualified health or mental-health professional is essential. Furthermore, commentaries addressing suicide among family caregivers warn that suicidal ideation can occasionally occur within this vulnerable population, and that accessing specialized mental health care can often prove exceedingly difficult.
The problem is capacity, not commitment
Caregiver burnout is frequently mischaracterized as a coping failure, leading to well-meaning platitudes such as meditating better, exercising more, staying positive, or taking a relaxing bath. While those actions may feel pleasant in the moment, they fail to answer the larger, more structural question: Has the overall care load fundamentally exceeded the time, financial resources, knowledge, backup systems, and recovery periods available to the caregiver? When human capacity is the true bottleneck, adding yet another self-care assignment often becomes just one more task the individual feels they are failing to finish.
This pressure is particularly acute during midlife. Caregivers in this demographic are frequently coordinating an aging parent’s complex care while simultaneously raising children, striving to protect their careers, and watching retirement costs move rapidly closer. A national study examining sandwich-generation caregivers highlighted significant financial strain stemming from the combined costs of child-rearing, elder-care expenses, and employment opportunity costs. While the study did not prove that every caregiver in the sandwich generation inevitably experiences burnout, it powerfully demonstrated that the underlying pressure is a structural reality rather than a private attitude problem.
The necessary reframe is direct: do not ask how to tolerate the same overwhelming care load more gracefully. Instead, ask which specific part of that load can be made safer, clearer, smaller, shared, or professionally supported.
Shifting this perspective turns generalized guilt into actionable operational decisions. A comprehensive life audit can reveal precisely where caregiving responsibilities are simultaneously undermining a person’s health, professional life, finances, and personal relationships. Rather than using such an audit to generate an even longer list of self-improvement chores, it should be utilized to pinpoint the exact load-bearing pressure points.
Use Care Load Triage before adding another coping task
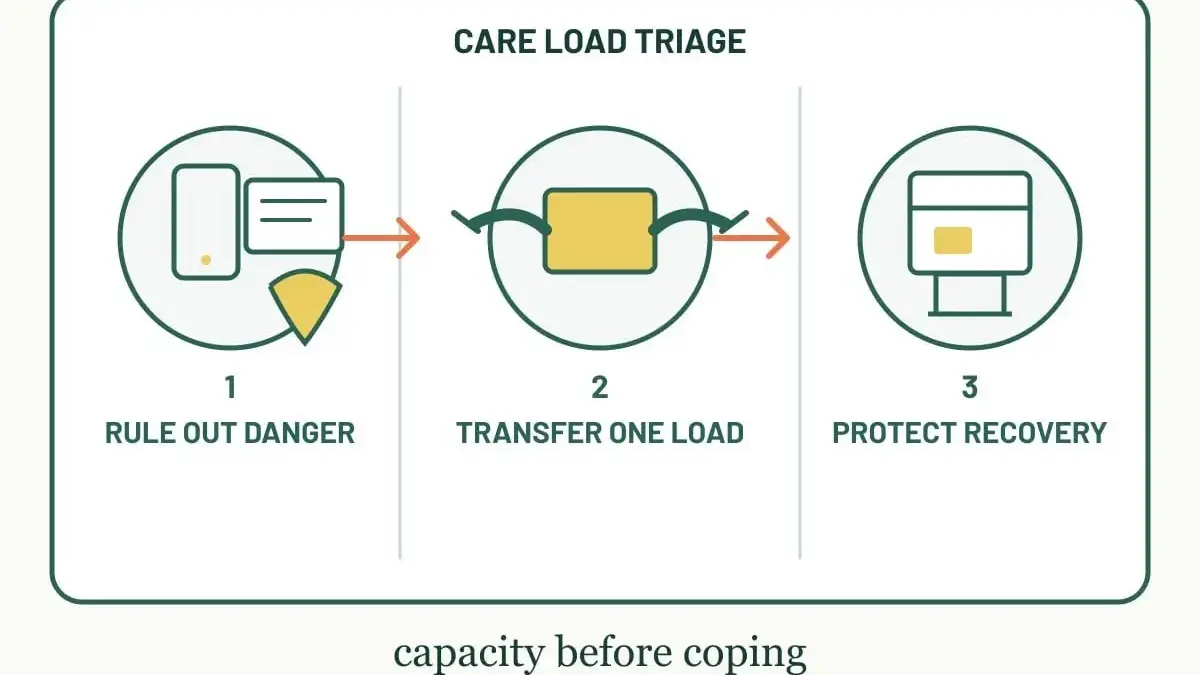
Care Load Triage functions as a practical three-part editorial tool designed to help overwhelmed individuals navigate immediate pressures. It involves ruling out immediate danger and persistent health concerns, transferring or simplifying at least one major load-bearing responsibility, and protecting one realistic recovery block. It is not a validated medical treatment or a promise of immediate recovery; its narrower purpose is to help individuals stop treating every single demand as equally urgent and instead choose one concrete change that reduces pressure within a 48-hour window.
The first step centers entirely on safety. Caregivers must evaluate whether both they and the person receiving care can navigate the immediate 24 hours safely. Essential questions include whether medications, food, physical mobility, constant supervision, transportation, and urgent appointments are adequately covered. It is also vital to assess whether extreme exhaustion or emotional distress is making activities like driving, lifting, medication management, or managing interpersonal conflict unsafe.

If the answer to any of these safety checks is uncertain or negative, seeking qualified help immediately is paramount. Local emergency services should be contacted in the face of immediate danger, while persistent symptoms or a declining ability to function warrant prompt consultation with a primary care physician or mental health professional. Individuals should never automatically assume that every physical or emotional symptom belongs strictly to caregiver burnout.
The second part of the triage process involves transferring at least one major load-bearing task. Vague offers of assistance like "let me know if you need anything" are well-meaning but fundamentally unusable during a crisis. True help must be converted into an owned task with a clearly defined scope and schedule.
When reliable family help is unavailable, organizational resources such as the Eldercare Locator can connect US families with local aging and disability services. Similarly, the ARCH National Respite Locator provides directories of respite resources, while the No Wrong Door initiative points individuals toward state-level access systems for long-term services and supports. Because availability, eligibility criteria, cost, and wait times vary significantly, these listings serve as valuable leads rather than absolute guarantees.
The third component requires protecting a dedicated recovery block. A true recovery block is never defined simply as whatever leftover time remains after everyone else’s needs have been settled. It must be given a clear owner, a definite start time, a specific end time, and reliable coverage. Twenty minutes behind a closed door may be entirely realistic for one household, just as a two-hour walk, a scheduled therapy appointment, a block of uninterrupted sleep while someone else monitors the phone, or a single evening free from care administration may work for another.
While protecting time will not unilaterally repair an impossible care arrangement, it can create enough cognitive and physical distance to clearly recognize what structural changes must be made.
Notice the signs before care becomes impossible
For individuals who search for answers about caregiver burnout because a particularly rough day has frightened them, the key is to look for consistent changes across several distinct areas of life rather than relying on a rigid numerical checklist. It is vital to notice what is becoming increasingly frequent, worsening, or unsafe: profound exhaustion that normal rest fails to shift, a mounting sense of dread before routine care tasks, growing irritability, emotional distance, forgotten steps in daily routines, missed workdays, social isolation, or a complete loss of interest in anything outside the caregiving role. Documenting these patterns and sharing them with a qualified professional is a critical step.
These warning signs do not automatically prove caregiver burnout; many require careful medical attention because identical patterns can equally reflect clinical depression, anxiety disorders, underlying sleep disorders, medication side effects, or physical illnesses. Furthermore, while generic burnout recovery stages can sometimes help explain why energy, attention, and emotional availability do not always return simultaneously, caregiver burnout itself features no validated universal staging model. Context-specific studies involving end-of-life caregiving provide valuable insights into specific situations, but they do not constitute a general burnout ladder.
What a 48-hour load reset can look like
A 48-hour load reset is not designed to miraculously solve caregiver burnout overnight. Instead, it replaces vague promises of self-care with realistic actions grounded in human capacity. Within a two-day window, a caregiver identifies their riskiest operational gap, assigns a new owner or smaller scope to a single task, and schedules one genuinely covered recovery block. The resulting changes may be modest, but they serve to test whether accumulated pressure can actually be shifted.
Consider the example of Dana, a 49-year-old corporate manager who balances leading a team, assisting her father following a stroke, and raising a teenager at home. She routinely skips lunch and spends her Sundays catching up on complex insurance paperwork. When her brother asks if he can help with anything, she instinctively replies that she has everything under control.
Upon conducting a brief load reset, Dana writes down every recurring care task on a single page and circles the three tasks that carry severe consequences if missed. She realizes that prescription pickups are already covered, but medical transport is not, and that endless calls to insurance companies consume hours of her week while rarely being genuinely urgent.
She asks her brother to take over Thursday medical transport duties for the upcoming month, including managing the wheelchair and appointment notes. She consolidates her insurance phone calls into a single, strictly limited 45-minute block on Friday evenings. Her designated recovery block is modest: a quiet Wednesday dinner with her phone deliberately left at her brother’s house.
Marcus, a 52-year-old caregiver with no local siblings, faces a different operational reality. His first task transfer involves contacting the Eldercare Locator, asking his father’s medical clinic whether a social worker or care manager is available on staff, and asking his employer one precise question regarding schedule flexibility. He utilizes firm communication boundaries, stating plainly that while he can handle the pharmacy run today, he cannot also cover the demanding evening visit.
Neither plan guarantees immediate recovery, but both successfully expose the next operational constraint, helping caregivers determine where formal support doors exist and where critical gaps remain.
What if no one else will help?
When no caregiver support is immediately forthcoming, individuals must take care not to turn that systemic lack of support into a personal mandate to become limitless. It is essential to separate unwilling relatives from genuinely unavailable services, unaffordable care options, and routine tasks that truly demand the caregiver’s personal presence. Documenting these structural gaps allows caregivers to approach clinicians, social workers, aging or disability navigators, employers, schools, faith communities, or local agencies with precise questions. While some doors will inevitably close, having a clear map of the landscape remains vital.
When rural access barriers, prohibitive costs, family conflicts, a loved one’s refusal of assistance, or exceptionally complex care requirements keep the overall load stubbornly high, no morning routine or productivity hack will erase the structural shortage. Returning consistently to the core principles of triage—ruling out immediate danger, transferring what can be shared, and fiercely protecting basic recovery—represents calm, disciplined management rather than frantic burnout hustle.
Making a single load-reducing move today begins with acknowledging that understanding the nature of caregiver burnout helps individuals choose their first practical step without feeling pressured to redesign their entire existence. By writing down the single task creating the greatest risk or repeated pressure during the week, a caregiver can decide whether it requires professional assessment, a new owner, a smaller scope, or protected time. Sending one precise request or making one phone call can initiate the process of sharing a burden. Caregivers do not have to prove their love and dedication by making their own human capacity entirely invisible.



Leave a Reply