
For millions of women navigating the midlife transition, the nightly struggle with rest carries a distinct and frustrating signature. Menopause sleep problems rarely manifest as a simple inability to wind down; instead, they show up at both ends of the night, making it difficult to fall asleep and even harder to stay asleep. Longitudinal data from the landmark Study of Women’s Health Across the Nation, which monitored 3,045 women aged 42 to 52 at enrollment, reveal that the statistical odds of experiencing both types of sleep disruption steadily rise across the entire menopausal transition.
The pattern quickly becomes a grueling routine. The nights repeat with mechanical precision, occurring even when nothing else in a woman’s external life has shifted. That specific combination is the ultimate tell, and it explains precisely why generic sleep hygiene advice routinely fails to address the underlying issue.
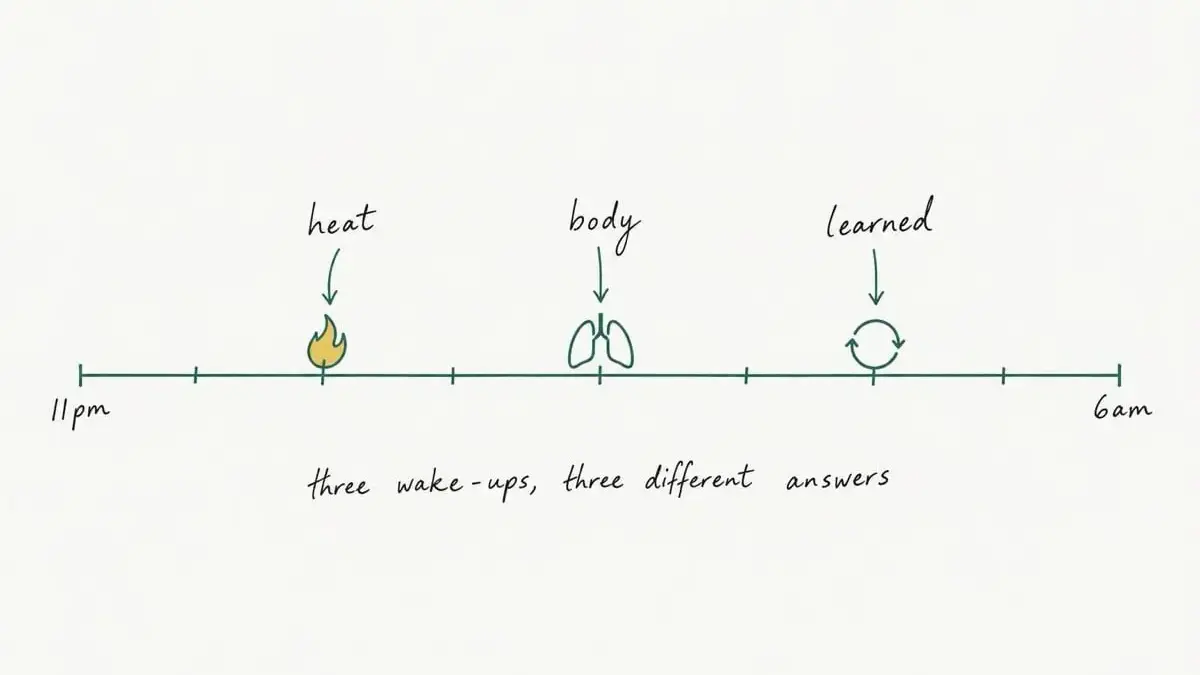
For a significant number of women, the second half of the night is the loudest disruptor, following a painfully familiar trajectory. Sleep arrives relatively easily by eleven, only for the individual to jolt awake at 2:40 in the morning—damp with sweat, kicking off the heavy covers, and then pulling them back up minutes later. Another awakening follows at 4:15, leading into a bleary-eyed alarm at six because professional responsibilities and early commutes do not pause for exhaustion.
By Thursday, the cumulative deficit takes its toll, manifesting as irritability with loved ones and the disheartening task of rereading the same professional email four times over. Secondary analyses tracking ten years of the same cohort found that self-reported insomnia symptoms affected 31 percent of women in early perimenopause during the first year, climbing to 39 percent by year ten. Among women in late perimenopause, the prevalence started at 32 percent and surged to 48 percent. These figures represent self-reported symptoms occurring at least three times a week rather than formal clinical diagnoses of insomnia, yet they clearly illustrate that midlife sleep disruption shifts across distinct stages and years. Still, understanding these numbers offers little comfort when staring at the ceiling at 3 a.m., feeling entirely isolated in the struggle.
Compounding the physical exhaustion is a psychological shift: many women report a developing dread of the bed itself. That emotional pivot is entirely new, and clinical experts note that it matters far more to long-term recovery than any supplement sitting on a bathroom counter.
Why the Usual Natural Remedies Keep Failing You
Traditional natural remedies for broken midlife sleep frequently fall short because they typically arrive as an unstructured list of options, completely lacking clear prioritization, known mechanisms, or any transparent grading of supporting scientific evidence. Melatonin serves as the clearest example of this disconnect. When researchers pool data across four randomized trials involving menopausal women, the overall effect on sleep quality fails to reach statistical significance. In scientific terms, this indicates uncertainty regarding its efficacy rather than definitive proof of failure, yet that nuance is rarely reflected on the colorful labels adorning store shelves.
Valerian root fares no better under rigorous scientific scrutiny. An umbrella review published in 2024 evaluated eight systematic reviews regarding the herb’s impact on sleep disturbances, ultimately judging the available evidence to be weak and inconclusive, showing no proven efficacy specifically for insomnia.
Confronted with these options, a woman might try one remedy, give it a fair two-week trial, feel no discernible difference, and quietly conclude that the failure rests with her own body. In reality, the problem lies in the approach. Patients are routinely handed an unvetted shelf of products and told to guess, which represents a profoundly ineffective strategy for treating menopause-related insomnia—a complex medical phenomenon driven by at least three entirely separate physiological causes.
Menopause Sleep Problems Are a Wake-Up Pattern, Not One Problem
Clinical researchers emphasize that menopause sleep problems do not stem from a single, uniform issue. Instead, they represent at least three distinct wake-up patterns wearing the exact same symptom: heat-driven waking, body-driven waking caused by factors such as disordered breathing, and learned waking that persists long after hot flashes have faded. Applying a remedy designed for one pattern does little to resolve the other two. Determining which specific pattern dominates a person’s nights is what transforms a random list of alternative treatments into an informed medical decision.
Heat-driven waking is the phenomenon most commonly associated with the transition, and its physical reality is well-documented. In a study tracking 168 midlife women using actigraphy devices, researchers found that 78 percent of objectively recorded nocturnal hot flashes coincided directly with an awakening episode. Furthermore, women were significantly more likely to be awake during the five minutes immediately following a flash than in the minutes leading up to it. While chronological concurrence does not definitively prove that every awakening is triggered exclusively by a flash, the statistical link is difficult to dismiss.
Body-driven waking represents the pattern most frequently overlooked by both patients and primary care providers. Data from the Sleep in Midlife Women Study demonstrated that the adjusted apnea-hypopnea index—a standardized measure of breathing disruptions during rest—was approximately 31 percent higher after menopause than before it. This metric tracks discrete respiratory events rather than counting new clinical diagnoses of sleep apnea. The critical takeaway lies in how the condition presents clinically: women suffering from obstructive sleep apnea frequently visit primary care clinics reporting complaints of insomnia, persistent fatigue, and low mood rather than classic symptoms like loud snoring, which remains a primary reason the condition goes widely undiagnosed in female patients.
Learned waking explains why many women remain wide awake at 3 a.m. years after their hot flashes have completely subsided. Over time, the bed transforms in the brain’s circuitry into a stressful location where an individual lies awake performing mental arithmetic about the upcoming day. This is no longer primarily a hormonal issue, making it the specific pattern backed by the strongest evidence for effective non-pharmacological treatment.
Categorizing these nightly disruptions into distinct groups serves as an organizational framework to help patients understand their symptoms, recognizing that real-world weeks frequently involve a mix of all three. Nevertheless, identifying the primary pattern points the way toward targeted clinical solutions.
Natural Remedies, Ranked by the Evidence Behind Them
When evaluated strictly by the strength of the clinical evidence supporting them, natural remedies for menopause-related sleep disturbances fall into a clear hierarchy: cognitive behavioral therapy for insomnia ranks first, regular exercise places second, and various dietary supplements sit a distant third. In a randomized controlled trial involving 106 midlife women suffering from frequent hot flashes and insomnia, telephone-delivered cognitive behavioral therapy for insomnia improved insomnia severity scores by roughly 5.2 points more than a menopause-education control group at eight weeks, with those gains successfully maintained at the 24-week mark. To date, no commercial supplement has demonstrated supporting evidence within that efficacy range.

Cognitive behavioral therapy for insomnia operates as a structured, short-term course of behavioral modification—typically spanning four to eight sessions—delivered by a trained clinician, therapist, or guided digital program. The intervention targets the mechanical drivers of sleeplessness: establishing a single, rigid wake time adhered to every day of the week, restricting time spent in bed to match actual sleep duration, getting out of bed rather than lying awake, and dismantling the anxiety-driven thought loops that plague the middle of the night.
Professional medical guidelines heavily favor this approach. The American College of Physicians recommends cognitive behavioral therapy for insomnia as the initial first-line treatment for all adults suffering from chronic insomnia, issuing a strong recommendation based on moderate-quality evidence, while positioning medication as a secondary option for shared decision-making if behavioral therapy alone proves insufficient. While that specific guideline covers chronic adult insomnia broadly rather than menopause exclusively, dedicated clinical trials confirm its strong applicability to midlife women experiencing hot flashes.
Medical societies issue an important caveat regarding these interventions: major clinical organizations recommend the full, multi-component version of cognitive behavioral therapy for insomnia while advising against relying on generic sleep hygiene tips as a stand-alone treatment. Consequently, maintaining a dark room, avoiding late screens, and cutting off evening caffeine—while sensible foundational habits—do not constitute a sufficient medical treatment on their own.
Exercise occupies the second tier of evidence-based interventions. Pooled individual-participant data across multiple clinical trials found that structured physical activity reduced Insomnia Severity Index scores by an average of 2.1 points relative to control groups. While a two-point drop represents a modest, genuine improvement rather than a complete cure, it remains a worthwhile pursuit, provided patients do not expect exercise alone to carry the entire therapeutic load.
Dietary supplements occupy the third and final tier, with their specific evidence limitations attached. Healthcare providers urge caution because botanical products frequently interact with prescription medications and with one another, necessitating a careful review with a physician or pharmacist before initiation.
Regarding the ubiquitous advice to cool the bedroom environment, clinical researchers note a distinct lack of controlled evidence demonstrating that ambient room temperature directly treats menopausal insomnia. While studies on healthy adults show that gently warming the skin of the trunk and upper legs can slightly shorten the time it takes to fall asleep, that research did not specifically examine menopause or nighttime cooling. Therefore, experts suggest viewing cool bedding and bedroom fans as tools for physical comfort rather than clinical treatment, noting that a night sweat is inherently less miserable when an individual is not trapped beneath heavy blankets, even if a thermostat cannot dismantle a 3 a.m. thought loop.
What One Week of This Actually Looks Like
In practical daily life, implementing an evidence-based approach to midlife sleep disruption is remarkably straightforward. Patients are advised to select a single wake time and hold it rigidly, including weekends. Each morning involves recording three simple data points: the approximate hour of waking, whether a heat event was involved, and whether any respiratory issues—ranging from partner-reported snoring to persistent daytime fatigue—occurred. Halting the constant addition of new, unproven interventions allows a personal sleep log, rather than a supplement label, to clarify which wake-up pattern is driving the disruptions.
Consider two hypothetical midlife profiles illustrating this diagnostic fork. Tricia, aged 49 in early perimenopause, logs four nocturnal wakings over seven nights, three of which involve soaked sheets requiring a change and immediate use of a fan, with no mention of breathing irregularities. Her pattern is clearly heat-driven. Her management strategy avoids purchasing a shelf of new products; instead, she fixes her wake time at 6:15, incorporates regular walks, utilizes breathable bedding, and maintains a concise note for her next medical appointment detailing the exact frequency of her hot flashes.
Marlene, aged 54 and two years past her final menstrual period, finds her hot flashes have largely subsided, yet she continues to wake up at 3:10 a.m. Her sleep log reveals zero heat events but highlights a persistent habit of lying awake for 90 minutes composing mental to-do lists for the following day. However, her breathing column is not blank; her husband has mentioned snoring on multiple occasions, and she frequently finds herself dozing off in front of the television by early evening. Her log points toward two distinct clinical actions: discussing cognitive behavioral therapy for insomnia to address her learned behavioral patterns, and raising the concerns regarding snoring and daytime sleepiness during the exact same medical appointment rather than dismissing them as ordinary fatigue. In the interim, she adopts the practice of leaving the bedroom after 20 minutes of wakefulness to break the mental association between her bed and active worrying.
Maintaining this basic log for a single week before altering any routines prevents the common pitfall of simultaneously adopting magnesium supplements, blackout curtains, expensive pillows, and sleep tracking apps, which usually obscures the true source of relief.
When This Needs a Clinician, Not a Remedy
Medical authorities emphasize that persistent sleep disruptions in midlife are frequently not simple lifestyle or remedy problems. Symptoms such as loud snoring, breathing that repeatedly stops and starts, gasping or choking sensations during sleep, and chronic daytime exhaustion are established indicators of sleep-disordered breathing. Major health organizations advise scheduling a physician consultation for these specific signs rather than experimenting down a supplement aisle. The same professional threshold applies to sleep difficulties occurring at least three times a week for a duration of three months or longer, meeting the clinical criteria for chronic insomnia.
Clinicians caution that dismissing chronic midlife sleep disruption with the phrase "it’s just menopause" is the single assumption most likely to delay proper care for months or years. Because sleep apnea and related respiratory disorders frequently manifest in women through atypical symptoms like insomnia, fatigue, and low mood rather than classic snoring, professional medical evaluation is essential.
For women whose sleep disruption remains tightly coupled with vasomotor symptoms, hormone therapy remains a viable subject for clinical discussion. Position statements from professional organizations like The North American Menopause Society identify hormone therapy as the most effective systemic treatment for moderate to severe hot flashes and night sweats, noting subsequent improvements in sleep quality when those disturbances are directly tied to vasomotor events. Hormone therapy is not classified as a standalone treatment for primary insomnia, and its suitability requires an individualized benefit-risk assessment conducted by a qualified healthcare professional.
Ultimately, addressing midlife sleep disturbances begins not with purchasing an array of unverified commercial products, but with patient observation. Establishing a consistent morning wake time, tracking the nature of nighttime awakenings for a single week, and bringing structured data to a medical appointment provides the foundation needed to replace guesswork with effective clinical care.
Leave a Reply