
For millions of women navigating the menopausal transition, nighttime disturbances do not feel like ordinary fatigue. Instead, they manifest as a specific disruption occurring at both ends of the night: it becomes markedly harder to fall asleep initially and significantly harder to stay asleep through the early morning hours. Data from the landmark Study of Women’s Health Across the Nation (SWAN), which enrolled 3,045 women aged 42 to 52, demonstrates that the statistical odds of experiencing both types of sleep trouble rise steadily across the menopausal transition.
The repetitive nature of these nights—often occurring when no other significant variables or stressors have changed in a woman’s daily routine—serves as a primary indicator of midlife endocrine shifts. This distinct pattern is precisely why generic sleep advice frequently fails to provide relief. For a substantial number of women, the second half of the night is the loudest disruptor. A typical scenario involves falling asleep relatively easily by eleven o’clock, only to wake up abruptly at 2:40 a.m. feeling damp, kicking off the covers, and subsequently pulling them back on as body temperature fluctuates, followed by another awakening at 4:15 a.m., and finally waking for the day at six o’clock despite profound exhaustion because professional and personal obligations demand it.
By the time Thursday arrives, chronic sleep deprivation takes its toll, manifesting as irritability with loved ones and the cognitive fatigue of rereading a single work email four separate times. A secondary analysis tracking ten years of the same SWAN cohort revealed that self-reported insomnia symptoms occurred in 31 percent of women during early perimenopause in the first year, climbing to 39 percent by year ten. Among women in late perimenopause, the prevalence started at 32 percent and rose to 48 percent over the same duration. These figures reflect self-reported symptoms experienced at least three times a week rather than clinically diagnosed insomnia, and they fluctuate by menopausal stage and year. Nevertheless, they highlight that midlife women suffering through the quiet hours of 3 a.m. are experiencing a widespread physiological phenomenon rather than an isolated personal failure. Over time, this recurring cycle fosters a new and distressing psychological hurdle: women begin to dread the bed itself. That psychological shift carries far more weight in the persistence of insomnia than any over-the-counter supplement found on a pharmacy shelf.
Why the Usual Natural Remedies Keep Failing You
Natural remedies aimed at fixing broken midlife sleep frequently fail because they are typically presented as an unranked menu of options lacking clear mechanisms of action or rigorous evidentiary grading. Melatonin offers a prime example of this disconnect. When pooled across four randomized clinical trials involving menopausal women, its measurable effect on overall sleep quality was found not to be statistically significant. In scientific terms, this indicates uncertainty regarding its efficacy rather than definitive proof of failure, yet that nuance is rarely communicated clearly on product labels.
Valerian root fares no better under scientific scrutiny. An umbrella review published in 2024 synthesized eight systematic reviews evaluating valerian for sleep disturbances and concluded that the supporting evidence was weak or inconclusive, showing no reliable evidence of efficacy for insomnia. Consequently, when an individual tries one of these remedies, dedicates two weeks to the regimen, notices no tangible improvement, and quietly blames themselves for the failure, they are misattributing the root cause. Consumers are typically handed a crowded retail shelf and told to guess, which represents an ineffective strategy for treating menopause-related insomnia—a complex condition driven by at least three distinct physiological and behavioral causes.
Menopause Sleep Problems Are a Wake-Up Pattern, Not One Problem
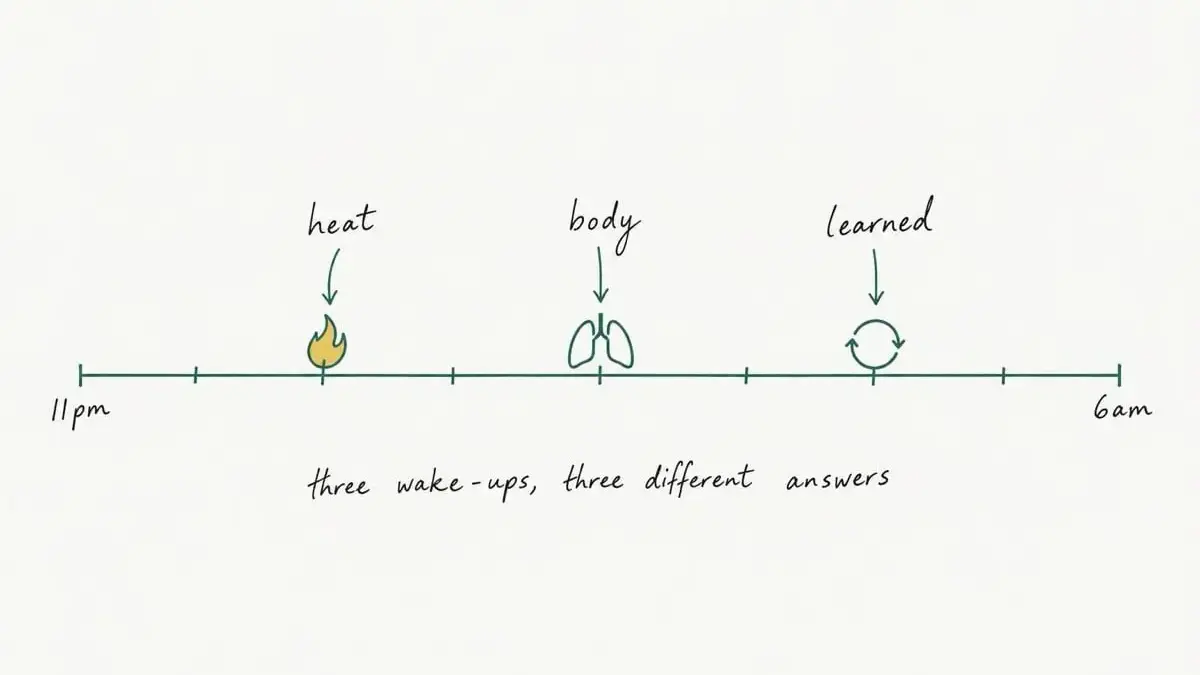
Menopause sleep problems are not a monolithic issue. Clinical observations indicate they comprise at least three distinct wake-up patterns wearing the same outward symptom: heat-driven awakenings, body-driven awakenings rooted in physiological issues such as disordered breathing, and learned awakenings that persist long after vasomotor symptoms like hot flashes have subsided. A remedy tailored exclusively to one of these patterns will inherently do little to resolve the other two. Identifying which specific pattern dominates a person’s nights is the crucial step that transforms an overwhelming list of remedies into a targeted medical and behavioral strategy.
Heat-driven waking is the mechanism most commonly associated with menopause, and its physiological basis is well-documented. In a study monitoring 168 midlife women using actigraphy, 78 percent of objectively recorded nocturnal hot flashes coincided directly with an awakening episode. Furthermore, women were significantly more likely to be awake during the five minutes immediately following a hot flash than in the minutes preceding it. While chronological concurrence does not strictly prove that every awakening initiates with a flash, the correlation remains difficult to dismiss.
Body-driven waking represents a pattern that is frequently missed in primary care settings. Data from the Sleep in Midlife Women Study revealed that the adjusted apnea-hypopnea index was approximately 31 percent higher after menopause than before it. This metric measures measurable breathing events during sleep rather than counting new clinical diagnoses of sleep apnea. What makes this finding clinically significant is how the condition presents in women: individuals with obstructive sleep apnea often report symptoms of insomnia, daytime fatigue, and low mood rather than loud snoring, which serves as a primary reason why sleep-disordered breathing remains vastly underdiagnosed in female patients.
Learned waking explains why many women remain wide awake at 3 a.m. years after their hot flashes have completely faded. Over time, the bed transitions from a place of rest into an environment associated with wakefulness and mental arithmetic concerning the demands of the following day. This particular pattern is no longer driven by fluctuating hormones, yet it is paradoxically the pattern backed by the most robust, evidence-based non-pharmacological treatments available. While categorizing nights into these three distinct groups serves as an organizational framework rather than a rigid clinical classification—and real-world weeks frequently feature overlapping symptoms—the categorization remains clinically useful because each distinct group points toward a different therapeutic next step.
Natural Remedies, Ranked by the Evidence Behind Them
When evaluated strictly by the strength of supporting scientific evidence, natural and non-pharmacological interventions for menopause sleep problems follow a clear hierarchy: cognitive behavioral therapy for insomnia (CBT-I) ranks first, regular physical activity ranks second, and dietary or herbal supplements occupy a distant third. In a randomized clinical trial involving 106 midlife women experiencing frequent hot flashes and insomnia, telephone-delivered CBT-I reduced insomnia severity scores by approximately 5.2 points more than a menopause-education control group at eight weeks, with these therapeutic gains successfully maintained at the 24-week follow-up mark. No available supplement possesses clinical trial evidence approaching that magnitude.
The evidence underpinning each tier of this hierarchy is derived from rigorous clinical research. CBT-I functions as a structured behavioral treatment rather than a collection of casual lifestyle tips. Typically delivered over four to eight sessions by a trained clinician, therapist, or guided digital program, CBT-I targets the core mechanics of sleep: maintaining a single, fixed wake time every day, restricting time spent in bed to closely match actual sleep duration, getting out of bed rather than lying awake during the night, and systematically dismantling the cognitive thought loops that dominate the early morning hours.
Professional medical organizations endorse this approach. The American College of Physicians recommends CBT-I as the initial treatment of choice for all adults suffering from chronic insomnia, issuing a strong recommendation based on moderate-quality evidence, with pharmacotherapy considered only as part of a shared decision-making process if behavioral therapy alone proves insufficient. While that specific guideline broadly encompasses adults with chronic insomnia rather than exclusively focusing on menopause, clinical trials specifically involving midlife women with hot flashes and insomnia validate its efficacy within this demographic.

Important clinical caveats apply to lifestyle modifications. The American Academy of Sleep Medicine recommends the comprehensive, multicomponent version of CBT-I while explicitly advising against relying on basic sleep hygiene measures as a standalone treatment. Consequently, maintaining a dark room, eliminating late-night screen time, and avoiding afternoon caffeine—while foundational—do not constitute adequate treatment on their own; they merely represent the baseline floor of healthy habits.
Physical activity occupies the second tier of evidence. Pooled individual-participant data across four trials conducted by the Menopause Strategies: Finding Lasting Answers for Symptoms and Health (MsFLASH) network demonstrated that structured exercise reduced Insomnia Severity Index scores by an average of 2.1 points relative to control groups. While CBT-I produced the largest reduction at 5.2 points, a two-point improvement represents a meaningful, albeit modest, clinical benefit that is worth implementing while recognizing it cannot carry the entire therapeutic burden alone.
Supplements occupy the third tier, with clinical data demonstrating varying degrees of uncertainty or weak support. Because dietary supplements can interact unpredictably with prescription medications and with one another, medical professionals advise patients to consult a physician or pharmacist before introducing any new supplement into their routine.
Regarding the ubiquitous advice to lower bedroom temperatures, a review of clinical literature reveals a lack of controlled evidence demonstrating that room temperature alone effectively treats menopausal insomnia. Studies examining skin warming in healthy adults indicate that minor increases in skin temperature can marginally shorten sleep-onset latency, but this research was not specific to menopause or cooling environments. Consequently, maintaining a cool bedroom, utilizing a fan, and selecting breathable bedding should be viewed as comfort measures to mitigate the misery of night sweats rather than definitive treatments for hormonal insomnia. A household thermostat cannot dismantle a 3 a.m. cognitive thought loop.
What One Week of This Actually Looks Like
In practical terms, adopting an evidence-based approach to midlife sleep disruption is systematic. A patient begins by selecting a single, consistent wake time and holding it rigidly every day of the week, including weekends. Each morning involves recording three specific data points: the hour of waking, whether thermal discomfort or heat was involved, and any observations related to breathing or daytime fatigue. Ceasing the constant addition of new supplements or wellness interventions allows the daily log—rather than product marketing claims—to reveal which specific wake-up pattern is dominating the night.
To illustrate how this functions in practice, consider two hypothetical clinical profiles. Tricia, aged 49, is in early perimenopause. Her sleep log reveals four nocturnal awakenings over seven nights, three of which required changing damp sheets and turning on a fan, with no abnormalities noted in the breathing column. Her pattern is clearly heat-driven. Her management strategy avoids a confusing array of eight simultaneous changes; instead, she maintains a fixed wake time at 6:15 a.m., incorporates regular walks, utilizes breathable bedding, and prepares a concise summary for her next physician’s appointment detailing the frequency of her night sweats. She purchases no new products. Furthermore, her log converts vague frustration into precise clinical data: four nights out of seven, featuring three instances of night sweats, persisting over an eleven-week period.
Marlene, aged 54, is two years past her final menstrual period. Her vasomotor hot flashes have largely subsided, yet she continues to wake consistently at 3:10 a.m. Her log demonstrates an absence of heat-related symptoms accompanied by a persistent behavioral habit of lying in bed for 90 minutes composing mental to-do lists for the following day. However, her breathing column is not empty; her partner has noted episodes of snoring, and she frequently falls asleep on the living room sofa by 8 p.m. Consequently, her log yields two distinct next steps: consulting her physician regarding CBT-I to address the learned behavioral wake pattern, and concurrently discussing her snoring and daytime sleepiness rather than dismissing them as general midlife exhaustion. In the interim, she breaks the behavioral loop by getting out of bed after twenty minutes of wakefulness to avoid reinforcing the psychological association between the bed and mental alertness.
Both individuals maintain their logs for a full week before implementing any changes. This disciplined approach avoids the common pitfall of simultaneously adopting magnesium supplements, blackout curtains, specialized pillows, and sleep-tracking applications, which ultimately obscures which intervention, if any, provided relief.
When This Needs a Clinician, Not a Remedy
Certain nocturnal symptoms indicate that sleep disruption has moved beyond the scope of lifestyle remedies or over-the-counter options. Loud snoring, breathing that repeatedly stops and starts, gasping or choking sensations during sleep, and persistent, severe daytime fatigue are recognized by major health authorities as primary indicators of obstructive sleep apnea. Medical guidance consistently recommends consulting a physician for these symptoms rather than experimenting with supplement aisles. Similarly, sleep difficulties occurring at least three times per week for three months or longer meet the established diagnostic threshold for chronic insomnia defined by the American Academy of Sleep Medicine.
Attributing ongoing sleep disturbances solely to the assumption that "it’s just menopause" frequently delays proper diagnosis and treatment by months or years. Because sleep-disordered breathing in women frequently presents as insomnia, fatigue, and low mood rather than classic heavy snoring, clinical evaluation is essential.
For women experiencing severe vasomotor symptoms, hormone therapy remains a viable clinical discussion. Position statements from the North American Menopause Society identify hormone therapy as the most effective pharmacological treatment for moderate to severe hot flashes and night sweats, noting subsequent improvements in sleep quality when disturbances are directly linked to those vasomotor symptoms. Hormone therapy is not prescribed as a standalone treatment for primary insomnia, and its suitability requires an individualized benefit-risk assessment conducted by a qualified healthcare provider.
Start With One Night, Not Eight Changes
Establishing a clear path forward begins with defining a consistent wake time before attempting any therapeutic intervention. Placing a notebook by the bedside to record the hour of waking, the presence of thermal discomfort, and any notes regarding breathing or daytime fatigue for seven consecutive nights provides foundational data. Maintaining a single wake time without introducing a confusing cascade of new routines avoids the common cycle of failed wellness experiments. A structured sleep log serves as an accessible diagnostic tool, translating generalized complaints into concrete information that enables clinicians to recommend targeted, evidence-based treatments.



Leave a Reply