
For millions of women navigating the menopausal transition, nighttime disruptions do not arrive as a gentle invitation to rest. Instead, they manifest as a frustrating double-edged sword: the agonizing difficulty of initially falling asleep compounded by the exhaustion of repeatedly waking up throughout the night. Data from the landmark Study of Women’s Health Across the Nation (SWAN), which meticulously followed 3,045 women aged 42 to 52 at enrollment, reveal that the odds of experiencing both types of sleep trouble steadily rise across the menopausal transition.
The pattern quickly becomes a grueling routine. The nights repeat with clockwork precision, often against a backdrop of a life that has otherwise remained entirely unchanged. This specific combination—the cyclical waking, the lack of external life stress to explain it, and the sheer persistence of the exhaustion—is the primary tell of midlife hormonal disruption. It is precisely why generic, one-size-fits-all sleep advice routinely bounces off midlife women, leaving them feeling isolated and unheard by standard wellness prescriptions.
For a significant number of women, the second half of the night is dominated by a familiar, disruptive physical sequence. They may fall asleep easily enough by eleven o’clock, only to jolt wide awake at 2:40 a.m. feeling damp, instinctively kicking the covers off before pulling them back up as a sudden chill sets in. Another wakeful episode often strikes at 4:15 a.m., before the alarm finally sounds at six o’clock to start a workday that offers no grace for sleep deprivation.
By the time Thursday rolls around, the cumulative toll becomes impossible to mask. Women find themselves uncharacteristically short with the people they love and struggling through basic cognitive tasks, such as rereading the exact same work email four times just to comprehend its contents. Secondary analyses tracking ten years of the SWAN cohort highlight the widespread nature of this issue. Insomnia symptoms were reported by 31% of women in early perimenopause during the first year, climbing to 39% by year ten. Among women in late perimenopause, the prevalence started at 32% and rose sharply to 48%.
It is crucial to note that these figures represent self-reported symptoms occurring at least three times a week rather than formal clinical diagnoses of chronic insomnia, and they naturally fluctuate across different stages and years. Yet, understanding these numbers provides profound psychological reassurance to those who lie awake at 3 a.m., feeling entirely like outliers. Perhaps most concerningly, this persistent disruption breeds a new and insidious psychological reaction: women begin to actively dread the bed itself. That emerging dread matters far more to long-term recovery than any supplement sitting on a bathroom counter.
Why the Usual Natural Remedies Keep Failing You
Natural remedies for broken midlife sleep almost invariably fail because they arrive as an unstructured list of options, completely stripped of clear mechanisms, proper ordering, or any rigorous grading of underlying evidence. Melatonin serves as the clearest example of this phenomenon. When data is pooled across four randomized clinical trials involving menopausal women, the actual effect on sleep quality is found to be not statistically significant. In scientific terms, that means the evidence is uncertain rather than outright disproven, but that nuance is rarely printed on the label of a retail box.
Herbal alternatives fare no better under scientific scrutiny. Valerian root, a staple of natural sleep aisles, is in an even weaker position. An exhaustive umbrella review published in 2024 synthesized eight systematic reviews examining valerian for sleep disturbances and judged the existing evidence to be weak or inconclusive, finding no demonstrable evidence of efficacy specifically for insomnia.
Consequently, a typical patient tries one remedy, gives it a fair two-week trial, feels absolutely no relief, and quietly concludes that the failure rests entirely with her own body. In reality, the problem is not the individual; it is the flawed approach of being handed a crowded retail shelf and told to guess. Treating menopause insomnia—a complex physiological challenge driven by multiple distinct underlying causes—by blindly picking remedies is bound to yield frustration.
Menopause Sleep Problems Are a Wake-Up Pattern, Not One Problem
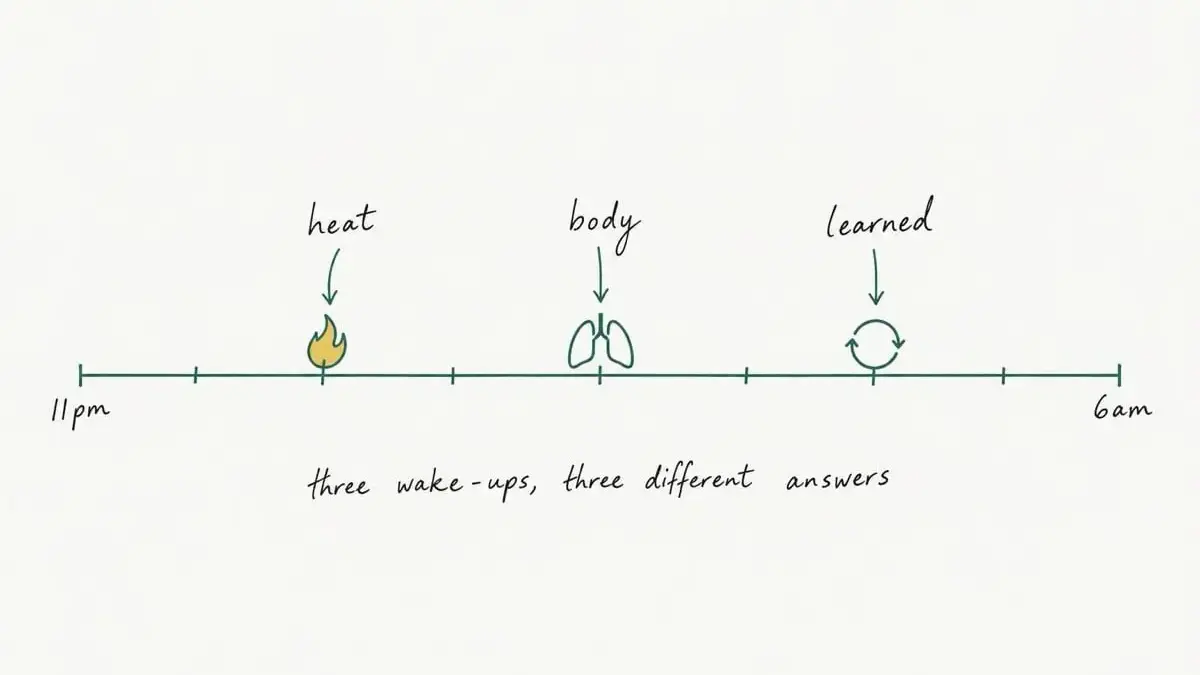
Clinical reality dictates that menopause sleep problems cannot be treated as a single, uniform issue. Instead, they represent at least three distinct wake-up patterns wearing the exact same symptom disguise: heat-driven waking, body-driven waking stemming from physiological shifts like disordered breathing, and learned waking that stubbornly outlives the initial hormonal triggers. A remedy aimed squarely at one of these patterns will inevitably do little to resolve the other two. Pinpointing which specific pattern dominates a person’s nights is the critical step that transforms a useless list of random tips into an actionable strategy.
Heat-driven waking is the phenomenon most commonly associated with menopause, and its physiological reality is well-documented. In an objective study tracking 168 midlife women using actigraphy, researchers found that 78% of objectively recorded nocturnal hot flashes coincided directly with a wake episode. Furthermore, women were significantly more likely to be awake in the five minutes immediately following a flash than in the minutes preceding it. While concurrence does not automatically prove that every single awakening initiates with a flash, the statistical link is difficult to dismiss.
Body-driven waking, on the other hand, represents the pattern that is most frequently missed by both patients and primary care providers. Data from the Sleep in Midlife Women Study demonstrated that the adjusted apnea-hypopnea index was roughly 31% higher after the menopausal transition than it was before. This metric measures physiological breathing events rather than simply counting new clinical apnea diagnoses. What makes this vital to recognize is how the condition presents clinically: women suffering from obstructive sleep apnea frequently present in primary care offices reporting classic insomnia, profound fatigue, and low mood rather than the stereotypical heavy snoring commonly associated with men. This atypical presentation is a primary reason why sleep-disordered breathing remains vastly undiagnosed in women.
Finally, learned waking explains the perplexing reality of why some women remain wide awake at 3 a.m. years after their hot flashes have completely faded. Over time, the bed transforms psychologically from a sanctuary of rest into a place where the mind lies trapped in anxious arithmetic about the obligations of the following day. This particular manifestation is no longer driven by fluctuating hormones; it is a conditioned behavioral response. Notably, it is also the pattern backed by the most robust, high-quality non-drug treatments available in modern medicine. While sorting nightly disruptions into these distinct categories serves primarily as an organizing framework rather than a rigid clinical classification—since real-world weeks often blend them together—doing so proves immensely useful because each group points toward a radically different next step.
Natural Remedies, Ranked by the Evidence Behind Them
When evaluated strictly by the strength of scientific evidence supporting their efficacy, natural and non-pharmacological interventions for menopause sleep problems fall into a clear hierarchy: cognitive behavioral therapy for insomnia (CBT-I) ranks first, regular physical exercise ranks second, and over-the-counter supplements trail as a distant third.
In a randomized clinical trial involving 106 midlife women suffering from frequent hot flashes and concurrent insomnia, telephone-delivered CBT-I improved insomnia severity scores by an impressive 5.2 points more than a menopause-education control group at the eight-week mark, and those significant gains successfully held steady at the 24-week follow-up evaluation. No dietary supplement or herbal extract possesses clinical trial evidence approaching that magnitude.
Examining the tiers individually reveals the stark contrast in proof. CBT-I is fundamentally a structured clinical treatment rather than a casual wellness tip. Usually delivered across four to eight sessions by a trained clinician, therapist, or a guided digital program, it targets the foundational mechanics of sleep. It establishes a single, unyielding wake time, restricts time spent in bed to closely match actual sleep duration, mandates getting out of bed rather than lying awake tossing and turning, and systematically dismantles the late-night thought loops that fuel chronic wakefulness.

Professional medical organizations endorse this approach. The American College of Physicians explicitly recommends CBT-I as the mandatory initial treatment for all adults suffering from chronic insomnia, issuing a strong recommendation backed by moderate-quality evidence, and positioning medication strictly as a secondary option for shared decision-making if behavioral therapy alone proves insufficient. While that specific guideline covers chronic insomnia across the adult population generally, the clinical trial focusing specifically on midlife women with hot flashes and insomnia bridges the gap directly to the menopausal demographic.
A vital distinction must be made regarding sleep hygiene. The American Academy of Sleep Medicine strongly recommends the comprehensive, multicomponent version of CBT-I while explicitly advising against relying on basic sleep hygiene tips as a stand-alone treatment. Consequently, the tidy checklist of dark-room protocols, screen bans, and afternoon caffeine limits that many women already follow is not a cure; it is merely the baseline foundation.
Exercise secures the second tier, supported by an honest and modest effect size. Pooled individual-participant data across four trials conducted by the MsFLASH research network revealed that regular exercise reduced Insomnia Severity Index scores by an average of 2.1 points relative to control groups. While 2.1 points represents a genuine and worthwhile clinical improvement, it is a modest shift—meaning exercise is well worth incorporating into a routine, but it cannot be expected to carry the entire therapeutic load on its own.
Supplements occupy the third and final tier. When examining these products through the lens of empirical data, the landscape is defined by weak or inconclusive findings. Furthermore, supplements routinely interact with prescription medications and with each other, making professional consultation with a clinician or pharmacist an essential prerequisite before ingestion.
What One Week of This Actually Looks Like
In practical daily life, adopting an evidence-based approach to midlife sleep disruption is remarkably unglamorous. It begins by choosing a single, consistent wake time and holding it firmly every day of the week, including Saturdays. Each morning, a patient records three simple pieces of data: the approximate time she woke up, whether physical heat played a role in the disruption, and whether any respiratory issues—ranging from partner-reported snoring to a pervasive, heavy daytime fatigue—emerged. By day five, this simple log replaces supplement marketing labels and clearly reveals which specific wake-up pattern is dominating the nights.
Hypothetical patient profiles illustrate how this diagnostic log alters the path forward. Consider Tricia, a 49-year-old in early perimenopause. Her nightly log over seven days records four wakings, three of which required changing damp sheets and turning on a bedside fan, with zero entries in the respiratory column. Her disruption is clearly heat-driven. Rather than making eight sweeping lifestyle changes, her strategy is streamlined: she establishes a fixed wake time of 6:15 a.m., incorporates daily walks, utilizes breathable bedding, and notes the frequency of her hot flashes to share with her doctor at her next visit. She purchases nothing new. Her log successfully translates the overwhelming emotional frustration of "I never sleep anymore" into precise clinical data: four out of seven nights disrupted, three involving night sweats, persisting for eleven weeks.
Alternatively, consider Marlene, a flourishing 54-year-old who is two years past her final menstrual period. Her hot flashes have largely subsided, yet she still finds herself wide awake at 3:10 a.m. Her log records no heat disturbances whatsoever, but reveals a persistent behavioral habit of lying awake in bed for ninety minutes mentally composing tomorrow’s to-do list. However, her respiratory column is not entirely blank; her husband has mentioned audible snoring on two occasions, and she frequently finds herself nodding off in front of the television by early evening.
Marlene’s log points toward two distinct next steps rather than a singular fix: she plans to consult her physician about CBT-I to address the learned behavioral wake pattern, while simultaneously raising the issues of nighttime snoring and daytime sleepiness in the same appointment rather than writing them off as mere fatigue. In the interim, she resolves to get out of bed whenever she has been awake for twenty minutes, stopping the unconscious conditioning that teaches her brain to associate the mattress with cognitive problem-solving.
Both women utilize the diagnostic log for a single week before altering any other variables, successfully avoiding the common trap of launching magnesium supplements, blackout curtains, expensive pillows, and sleep-tracking mobile applications all in the same week, which ultimately yields zero clarity. Moreover, both women consciously avoid viewing their broken sleep as a personal moral failing or a referendum on their self-discipline, recognizing that midlife sleep disruption frequently arrives alongside a constellation of concurrent physical and psychological shifts.
When This Needs a Clinician, Not a Remedy
Certain nocturnal presentations clearly transcend the realm of simple home remedies. Loud snoring, breathing that repeatedly stops and starts, sudden gasping or choking noises during the night, and pervasive, severe daytime fatigue are recognized as primary clinical indicators of sleep-disordered breathing. Major health authorities consistently advise consulting a physician regarding these symptoms rather than endlessly cycling through the supplement aisle.
Similarly, sleep difficulties that persist at least three times a week for a duration of three months or more meet the established clinical threshold for chronic insomnia defined by the American Academy of Sleep Medicine. Dismissing these persistent symptoms with the casual assumption that "it’s just menopause" is the single most common diagnostic pitfall, frequently costing patients months or years of unnecessary suffering. The empirical research linking midlife hormonal shifts to increased apnea indices underscores why insomnia, fatigue, and low mood must be investigated as potential manifestations of sleep-disordered breathing in women.
Hormone therapy also warrants careful consideration during these clinical consultations. Position statements from professional organizations, such as the North American Menopause Society, identify hormone therapy as the single most effective systemic treatment for vasomotor symptoms like hot flashes and night sweats, noting subsequent improvements in sleep quality when the underlying disturbance is directly tied to those physiological symptoms. However, hormone therapy is not prescribed as a standalone treatment for primary insomnia; its appropriateness depends entirely upon a personalized, comprehensive benefit-risk assessment conducted alongside a qualified healthcare provider.
Start With One Night, Not Eight Changes
For those grappling with the frustrations of midlife exhaustion, the path forward begins with simplicity rather than a sprawling consumer shopping list. Selecting a dedicated wake time before purchasing a single remedy establishes the primary anchor. Placing a simple notepad by the bed to record the hour of waking, the presence of heat, and any accompanying respiratory or daytime fatigue signs creates an invaluable baseline. Maintaining this uncomplicated log for seven consecutive days while holding a single wake time requires no financial investment, no mobile application, and no complex routine piled on top of an already exhausted system.
Ultimately, this straightforward log functions as an accessible diagnostic tool, cutting through the confusion of the supplement market and transforming vague complaints into concise, actionable clinical data that both patients and physicians can utilize to reclaim restorative rest.



Leave a Reply