
For millions of women navigating the menopausal transition, nighttime does not bring rest; it brings a frustrating routine of tossing, turning, and staring at the ceiling. Menopause sleep problems typically manifest at both ends of the night, making it exceptionally difficult to both fall asleep and stay asleep. Data from the landmark Study of Women’s Health Across the Nation (SWAN), which meticulously followed 3,045 women enrolled between the ages of 42 and 52, revealed that the odds of experiencing both types of sleep disturbances rise steadily across the entire menopausal transition.
When nights repeat themselves in this exhausting pattern and nothing else in your daily life has changed, it serves as a distinct telltale sign. This unique etiology is precisely why generic, one-size-fits-all sleep advice routinely fails midlife women.
For a significant number of individuals, the waking-up half of the night is the loudest and most disruptive, following a bitterly familiar script. A woman might fall asleep easily enough by eleven o’clock, only to jolt awake at 2:40 a.m., feeling damp and clammy, kicking off the heavy covers before pulling them back on shortly after. Another waking follows at 4:15 a.m., leading inevitably to an unrefreshed start at six o’clock because professional obligations and daily responsibilities demand attention regardless of how the night was spent.
By Thursday, the cumulative toll becomes glaringly obvious. Exhaustion manifests as a shortened temper with loved ones and the frustrating realization that a routine work email must be reread four separate times just to comprehend its basic contents. A secondary analysis tracking ten years of data from the same SWAN cohort painted a vivid picture of this progression, finding that self-reported insomnia symptoms occurred in 31% of women during early perimenopause in the first year, climbing to 39% by year ten. Among women in late perimenopause, the prevalence started at 32% and surged to 48%.
It is crucial to understand that these figures represent self-reported symptoms occurring at least three times a week rather than clinical insomnia diagnoses, and they fluctuate depending on the specific reproductive stage and year. Yet, recognizing these trends offers profound reassurance to anyone lying awake at 3 a.m. feeling entirely isolated.
Perhaps most insidiously, many women develop a deep, psychological dread of the bed itself. This development is entirely new, highly disruptive, and ultimately matters far more to long-term recovery than any expensive supplement sitting on a kitchen counter.
Why the Usual Natural Remedies Keep Failing You
Standard natural remedies prescribed for broken midlife sleep almost invariably fail because they are traditionally presented as an overwhelming, unstructured menu of eight different options devoid of clear ordering, underlying physiological mechanisms, or critical evaluations of scientific evidence.
Melatonin serves as the clearest example of this disconnect. When pooled across four randomized clinical trials specifically involving menopausal women, the actual effect of melatonin on overall sleep quality failed to reach statistical significance. In scientific terms, this denotes uncertainty rather than outright disproven efficacy, but that nuance is rarely captured on the colorful label of a retail box.
Valerian fares no better under scientific scrutiny. An extensive umbrella review conducted in 2024 synthesized eight distinct systematic reviews examining valerian for sleep disturbances and ultimately judged the supporting evidence to be weak or entirely inconclusive, showing no proven efficacy for treating insomnia.
Consequently, a typical patient will try one remedy, give it a trial period of two weeks, experience zero measurable relief, and quietly internalize the failure, deciding that the problem lies entirely within themselves. In reality, the fault rests with an unguided retail marketplace that hands consumers a crowded shelf and tells them to guess blindly—a remarkably ineffective approach to treating menopause-related insomnia, which actually stems from at least three distinct physiological causes.
Menopause Sleep Problems Are a Wake-Up Pattern, Not One Problem
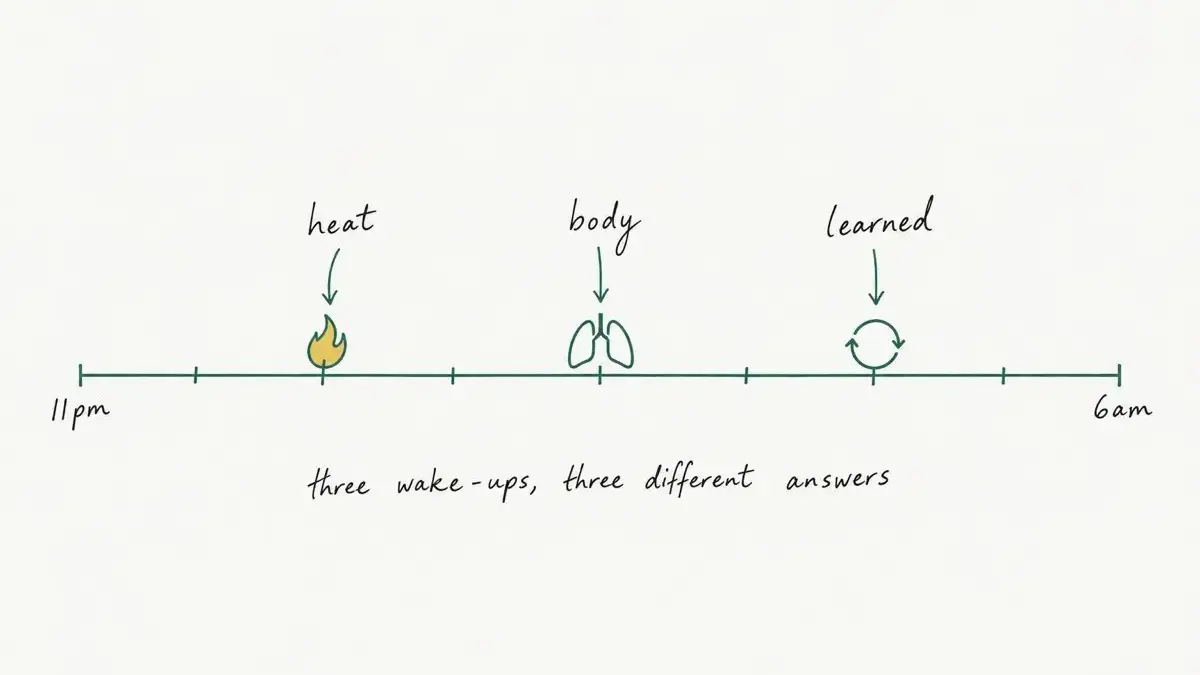
Clinical reality demonstrates that menopause sleep problems do not represent a single, uniform medical issue. Instead, they encompass at least three distinct wake-up patterns masquerading under the exact same subjective symptom: heat-driven waking, body-driven waking stemming from physiological issues such as disordered breathing, and learned waking that persists long after hot flashes have subsided. A remedy aimed squarely at addressing one specific pattern will naturally do very little to resolve the other two. Determining which of these patterns dominates a person’s nights is the critical step that transforms a haphazard list of internet remedies into a coherent, actionable strategy.
Heat-driven waking is the phenomenon everyone immediately pictures, and its physiological basis is well-documented. In a study monitoring 168 midlife women using actigraphy, 78% of objectively recorded nocturnal hot flashes coincided directly with a waking episode. Furthermore, women were significantly more likely to be awake during the five minutes immediately following a flash than in the minutes leading up to it. While mere concurrence does not definitively prove that every single awakening originates with a thermal surge, the clinical link remains exceptionally difficult to dispute.
Body-driven waking represents the pattern that is most frequently missed by primary care providers and patients alike. Data from the Sleep in Midlife Women Study revealed that the adjusted apnea-hypopnea index was approximately 31% higher after the menopause transition than before it. This metric measures measurable breathing disruptions rather than counting formal new apnea diagnoses. What makes this finding vital to understand is how the condition typically presents in clinical settings: women suffering from obstructive sleep apnea frequently visit their primary care physicians reporting classic symptoms of insomnia, profound fatigue, and low mood rather than the traditional symptom of heavy snoring. This atypical presentation is a primary reason why sleep-disordered breathing remains vastly underdiagnosed among women.
Learned waking explains why a substantial number of women remain wide awake at 3 a.m. years after their hot flashes have completely faded away. Over time, the bed transforms psychologically from a sanctuary of rest into a stressful environment where an individual lies awake performing mental arithmetic about the upcoming day. This specific phenomenon is no longer driven by fluctuating hormones, yet it represents the exact sleep disturbance backed by the strongest evidence for non-pharmacological treatment.
While sorting disruptive nights into these three distinct categories serves primarily as an organizational framework rather than a rigid clinical classification—and acknowledging that real-world weeks often blend them together—the categorization remains immensely useful. Each distinct group points directly toward a different, more appropriate clinical next step.
Natural Remedies, Ranked by the Evidence Behind Them
When evaluated strictly by the strength and quality of scientific evidence supporting them, natural remedies for menopause-related sleep problems fall into a clear hierarchy: cognitive behavioral therapy for insomnia (CBT-I) ranks first, regular physical exercise ranks second, and dietary or herbal supplements occupy a distant third.
In a randomized controlled trial involving 106 midlife women suffering from frequent hot flashes and co-occurring insomnia, telephone-delivered CBT-I improved insomnia severity scores by roughly 5.2 points more than a menopause-education control group at the eight-week mark, and those clinical gains were successfully maintained at the 24-week follow-up evaluation. To date, no over-the-counter supplement has produced scientific evidence matching that magnitude of improvement.
The hierarchy itself reflects an evidence-based assessment, and the robust data underlying each individual tier speaks for itself.
First: CBT-I, Which Is a Treatment, Not a Tip
Cognitive behavioral therapy for insomnia is structured as a short, intensive course of behavioral modification, typically spanning four to eight sessions delivered by a qualified clinician, a trained therapist, or a validated digital program. The intervention targets the core mechanics of sleep: establishing a single, immovable wake time held every day of the week, restricting time spent in bed to closely match the actual hours of sleep being achieved, getting out of bed rather than lying awake in frustration, and systematically dismantling the late-night thought loops that perpetuate insomnia.
Professional medical guidelines consistently point toward CBT-I as the premier intervention. The American College of Physicians formally recommends CBT-I as the initial, primary treatment for all adult patients suffering from chronic insomnia, issuing a strong recommendation based on moderate-quality evidence, while positioning medication as a secondary option for shared decision-making if behavioral therapy alone proves insufficient.
While that broader clinical guideline encompasses adults with chronic insomnia generally rather than focusing exclusively on menopausal women, the aforementioned clinical trial specifically targeted midlife women experiencing frequent hot flashes alongside insomnia.

A crucial distinction must be made regarding sleep hygiene. The American Academy of Sleep Medicine strongly recommends the comprehensive, multicomponent version of CBT-I while explicitly advising against relying on basic sleep hygiene tips as a standalone treatment. Consequently, the tidy checklist of maintaining a dark room, avoiding screens, and cutting off afternoon coffee—habits many women have already religiously adopted—does not constitute the treatment itself. Those practices merely represent the baseline floor of healthy habits.
Second: Exercise, With an Honest Effect Size
Pooled individual-participant data gathered across four clinical trials conducted by the Menopausal Strategies: Finding Another Link (MsFLASH) research network revealed that structured physical exercise reduced Insomnia Severity Index scores by an average of 2.1 points relative to control groups. While CBT-I produced the largest observed effect at 5.2 points, a two-point improvement remains a genuine, albeit modest, clinical benefit. It is an intervention well worth performing, provided expectations are kept realistic regarding its capacity to shoulder the entire burden of sleep restoration.
Third: Supplements, With Their Evidence Attached
Medical experts emphasize that supplements interact unpredictably with prescription medications and with each other, making it vital to review any herbal product with a clinician or pharmacist before initiating use. While retail markets offer numerous options, scientific evaluations of menopause-specific evidence for common remedies reveal significant limitations.
A Note on the Cool-Bedroom Advice
Nearly every popular article addressing midlife sleep disruption advises lowering the ambient temperature of the bedroom. However, comprehensive reviews fail to uncover controlled clinical evidence demonstrating that cooler room temperatures effectively treat menopausal insomnia.
Controlled studies examining healthy adults have shown that slightly warming the skin of the torso and upper legs by less than one degree Celsius can shorten sleep-onset latency by approximately three minutes. However, because that specific research was not conducted on menopausal women or focused on cooling mechanisms, it neither validates nor refutes the conventional bedroom cooling advice.
The absence of robust scientific proof should not be interpreted as definitive evidence against the practice. Maintaining a bedroom fan and breathable bedding remains worthwhile simply because surviving a severe night sweat is measurably less miserable when an individual is not trapped beneath heavy flannel. Ultimately, these adjustments should be viewed as measures of physical comfort rather than clinical treatments, and no home thermostat can successfully resolve a persistent 3 a.m. anxiety loop.
What One Week of This Actually Looks Like
In practical daily life, adopting an evidence-based approach to midlife sleep disruption is remarkably straightforward, though rarely glamorous. The process begins by selecting a single, consistent wake time and holding to it strictly, including Saturdays and Sundays. Each morning involves recording three simple data points on a piece of paper: the approximate time of waking, whether a thermal hot flash was involved, and whether any respiratory issues or daytime fatigue surfaced, ranging from heavy snoring noted by a partner to feeling utterly depleted throughout the entire day.
Crucially, the patient stops continuously adding new commercial interventions. By the fifth day, this personal log—rather than the marketing claims on a supplement bottle—clearly reveals which specific wake-up pattern is dominating the night.
To illustrate how this functions in practice, consider two hypothetical profiles. Tricia, a 49-year-old in early perimenopause, logs four disruptive wakings over seven nights, three of which involve drenched sheets requiring linen changes and immediate use of a bedroom fan, with zero abnormalities noted in her breathing column. Her pattern is unmistakably heat-driven. Her management plan avoids a sprawling list of eight lifestyle overhauls; instead, she establishes a fixed wake time of 6:15 a.m., incorporates daily walks, switches to breathable bedding, and logs the precise frequency of her nocturnal flashes to share with her doctor at her next scheduled visit. She purchases no specialized products.
Furthermore, Tricia’s log achieves something psychologically valuable by translating the vague distress of "I never sleep anymore" into concrete, quantifiable data that a clinician can readily evaluate: four nights out of seven, featuring three episodes of night sweats, persisting consistently for eleven weeks.
Marlene, aged 54 and two years past her final menstrual period, experiences virtually no hot flashes. Yet, she unfailingly wakes up at 3:10 a.m., her log showing zero thermal activity alongside a persistent habit of lying awake in bed for 90 minutes mentally organizing the next day’s to-do list. However, her breathing column is not entirely clear; her husband has mentioned audible snoring on two occasions, and she frequently catches herself dobbing off in front of the television by eight o’clock in the evening.
Consequently, Marlene’s logging yields two distinct next steps: consulting her physician regarding CBT-I to address the entrenched behavioral wake pattern, and concurrently raising the issues of nighttime snoring and daytime somnolence during the same medical appointment rather than dismissing them as ordinary fatigue. In the interim, she resolves to get out of bed whenever she has remained awake for roughly 20 minutes, refusing to continue teaching her brain to associate the mattress with cognitive problem-solving.
Both individuals maintain their logs for a full week before implementing any changes. That single discipline prevents the classic pitfall of launching magnesium supplements, blackout curtains, specialized pillows, and smartphone sleep tracking applications all in the same week, which makes it impossible to determine what, if anything, is working.
Neither reader treats these sleep disturbances as a personal failure of discipline. Broken sleep during the forties and fifties frequently arrives bundled alongside a host of other sweeping physiological and psychological shifts.
When This Needs a Clinician, Not a Remedy
Certain nocturnal symptoms signal that an individual is dealing with a formal medical condition rather than a simple lifestyle or remedy puzzle. Loud snoring, breathing that repeatedly stops and starts throughout the night, audible gasping or choking noises, and persistent, overwhelming daytime exhaustion are recognized as primary clinical indicators of sleep apnea. Major health authorities consistently advise consulting a qualified physician regarding any of these signs rather than continuing to experiment with over-the-counter remedies down the supplement aisle.
The same medical evaluation is warranted when sleep difficulties persist at a frequency of at least three nights a week for a duration of three months or longer—the established diagnostic threshold for chronic insomnia defined by the American Academy of Sleep Medicine.
While medical professionals do not diagnose or prescribe through general reporting, experts emphasize that dismissing persistent exhaustion with the assumption that "it’s just menopause" is the single most common error that can cost a patient months or years of unnecessary suffering. Research highlighting the increased prevalence of sleep-disordered breathing during midlife explains why insomnia, pervasive fatigue, and low mood frequently serve as the primary presenting symptoms of sleep apnea in women.
Hormone therapy warrants serious discussion during such medical appointments, representing a clinical decision best determined collaboratively with a personal physician. Position statements from professional organizations, such as the North American Menopause Society, identify hormone therapy as the single most effective pharmacological treatment for moderate to severe hot flashes and night sweats, noting subsequent improvements in sleep quality when nocturnal disturbances are directly tied to vasomotor symptoms.
However, hormone therapy is not designed to function as a standalone treatment for primary insomnia, and its suitability depends entirely upon an individualized assessment of potential medical benefits and personal risk factors.
Start With One Night, Not Eight Changes
Selecting an immovable wake time prior to purchasing any therapeutic remedy forms the foundational step toward restoring midlife rest. Placing a simple notepad by the bedside to record the hour of waking, the presence or absence of thermal heat, and any observations regarding breathing or daytime fatigue establishes a clear baseline. Maintaining this log for seven consecutive nights while keeping a single, fixed wake time and changing nothing else requires no financial investment, no smartphone applications, and no complicated routines stacked precariously on top of existing habits.
This straightforward sleep log serves as an exceptionally cost-effective diagnostic tool, bridging the gap between an overwhelming retail shelf of speculative natural remedies and a targeted, evidence-based strategy worth pursuing. Ultimately, clear and accurate personal data provides a physician with meaningful clinical insights far superior to vague complaints of poor sleep, paving the way for lasting relief.


