
At 9:40 p.m., after a full workday that included answering a teenager’s school messages, picking up a prescription for an aging father, and coordinating with an insurance company from a grocery store parking lot, millions of adults are told they need to make more time for self-care.
The advice is not inherently wrong, but it is fundamentally too small for the load.
For tens of millions of people, caregiving expands silently into every corner of life—swallowing work hours, sleep schedules, personal finances, marriages, parenting responsibilities, and individual health. Eventually, no single task looks impossible on its own, but the entire week does. A caregiver might still be managing every medical appointment and paying every bill on time, yet find themselves snapping at the people they love most, forgetting routine details, or feeling a numb emotional void when another request arrives.
That persistent pattern deserves structural attention rather than a superficial character judgment. What is commonly called caregiver burnout is a useful name for cumulative depletion under sustained care demands. It is not a formal diagnosis that can be confirmed from an online checklist, nor is it proof that an individual has stopped caring about their loved one.
For those facing immediate crises, safety concerns, or thoughts of self-harm, emergency services remain the critical first step. In the United States, individuals can call or text 988 to reach the Suicide & Crisis Lifeline. For those managing the slow, grinding erosion of everyday capacity, however, the challenge requires a deeper examination of systemic pressure rather than a simple reminder to relax.
What is Caregiver Burnout?
Caregiver burnout describes a pattern of physical, emotional, and mental depletion linked directly to sustained caregiving demands paired with insufficient support, control, or recovery time. It frequently manifests as deep exhaustion, emotional detachment, irritability, a sense of dread, cognitive mistakes, or a reduced ability to manage the ordinary routines of daily life. The term describes a lived experience rather than a standalone medical diagnosis, and very similar symptoms can stem from clinical depression, sleep disorders, medication side effects, or other underlying health problems that require professional medical assessment.
Academic frameworks for informal caregiving treat burnout not as a personal failure of resilience, but as the result of interacting conditions: the physical care setting, the caregiver’s available resources, the surrounding environment, how demands are appraised, and the nature of the relationship itself.
At the same time, burnout research carries real professional boundaries. A review published in the BMJ highlighted that, despite decades of academic study, no universally validated clinical diagnosis for burnout has been officially established. That reality does not make an individual’s distress imaginary; rather, it emphasizes that a convenient label should never replace a thorough clinical evaluation when symptoms persist, worsen, or actively interfere with personal safety and daily functioning.
The sheer scale of the issue underscores how widespread the phenomenon has become. According to estimates from AARP and the National Alliance for Caregiving, roughly 63 million adults in the United States—nearly one in four—provided ongoing care to an adult or child with a medical condition or disability. While that figure does not represent a direct burnout rate, it illustrates precisely how many households routinely carry an immense amount of labor that frequently remains invisible to the outside world.
Caregiver Stress, Burnout, and Compassion Fatigue Are Not Interchangeable
In professional and academic discussions, terms like caregiver stress, burnout, and compassion fatigue are frequently conflated, yet they describe distinct psychological phenomena. Caregiver stress represents the immediate strain of active care demands. Burnout describes the cumulative depletion that occurs when high demands continue over a prolonged period without adequate resources or recovery time. Compassion fatigue and secondary traumatic stress, by contrast, focus more specifically on the psychological impact of repeated exposure to another person’s physical or emotional suffering. Meanwhile, depression is a distinct clinical condition rather than simply a stronger word for burnout.
While these experiences frequently overlap in daily life, researchers have yet to draw clean clinical borders that allow a simple checklist to sort them safely. Studies examining medical professionals have found significant overlap among burnout, compassion fatigue, and secondary traumatic stress, alongside unresolved boundaries between burnout and clinical depression. Because those samples consisted of professionals rather than unpaid family caregivers, the exact concepts do not transfer perfectly, but the distinction remains useful for gaining direction rather than seeking a clinical diagnosis.
Individuals do not need the perfect medical label before asking for help. When persistent low mood, overwhelming hopelessness, panic attacks, severe sleep disruptions, chronic pain, increased substance use, or difficulties functioning begin to mount, contacting a healthcare or mental health professional is essential. Commentaries addressing mental health among family caregivers have repeatedly warned that suicidal thoughts can occur within this vulnerable population, and that accessing specialized mental health care can frequently be difficult.

The Problem Is Capacity, Not Commitment
Caregiver burnout is routinely treated as a coping failure, often met with well-intentioned advice to meditate better, exercise more, stay positive, or take a relaxing bath. While those actions may feel temporarily soothing, they fail to answer the core structural question: Has the actual care load exceeded the time, financial resources, professional knowledge, backup support, and recovery time available to the individual?
When capacity is the primary bottleneck, assigning yet another self-care task simply creates one more obligation that the individual feels they are failing to finish.
This pressure is particularly acute for adults in midlife. Many find themselves simultaneously coordinating complex medical care for an aging parent while raising children, protecting demanding careers, and watching the costs of their own retirement draw closer. National studies focusing on the "sandwich generation" have highlighted the severe financial strain caused by the simultaneous costs of child-rearing, elder care, and lost employment opportunities. While not every sandwich-generation caregiver experiences severe burnout, the structural data demonstrates that the pressure is an economic and logistical reality rather than a private attitude problem.
The necessary reframe is blunt: instead of asking how to tolerate an impossible care load more gracefully, caregivers must ask which specific parts of the load can be made safer, clearer, smaller, shared, or professionally supported. Shifting that perspective turns overwhelming guilt into actionable operational decisions. A comprehensive life audit can reveal precisely where caregiving is simultaneously pulling down health, work performance, personal finances, and relationships, serving as a tool to locate the true load-bearing points of daily life.
Navigating Care Load Triage
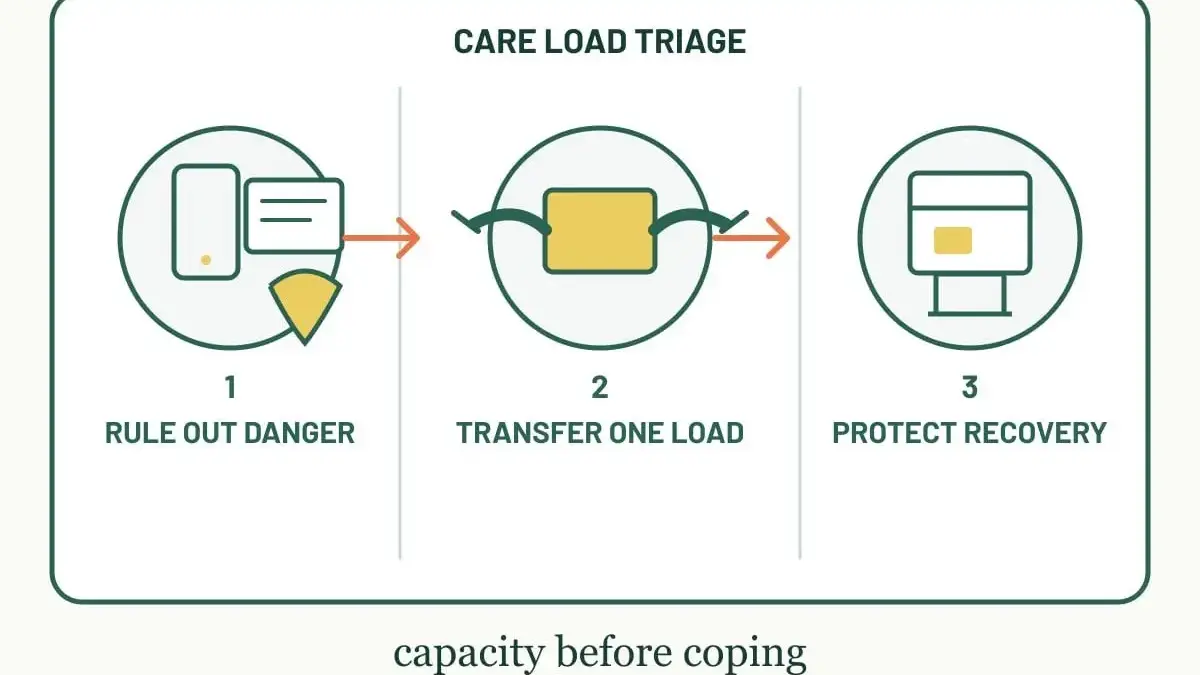
When facing overwhelming demands, many experts advocate for a structured approach known as Care Load Triage, which functions as an editorial and organizational tool rather than a validated clinical treatment. Its primary purpose is to help individuals stop treating every single daily demand as equally urgent and instead choose one meaningful change that reduces pressure within a short operational window.
The first priority is always ruling out immediate danger and persistent health concerns. Caregivers must evaluate whether both they and the person in their care can navigate the immediate future safely. This involves verifying that medications, food supplies, mobility assistance, supervision, transportation, and urgent medical appointments are properly covered, and ensuring that extreme exhaustion or emotional distress is not making activities like driving, lifting, or managing medications unsafe. If immediate safety is compromised, emergency services or qualified medical professionals must be contacted directly.
The second priority involves transferring at least one load-bearing responsibility. Vague offers of assistance from friends and family, such as letting someone know if they need anything, are rarely usable in high-stress situations. Assistance must be converted into an owned task with a defined scope and specific timeline, such as assigning a family member responsibility for specific medical transport days or pharmacy pickups. For families lacking local support networks, resources like the Eldercare Locator, the ARCH National Respite Locator, and state long-term services systems can help identify formal community assistance, though availability and wait times vary widely.
The third priority focuses on protecting a designated recovery block. Rather than treating recovery time as whatever scraps are left over after every other demand has been met, a recovery block requires an owner, a clear start and end time, and external coverage. Whether it is twenty minutes behind a closed door, a scheduled walk, a therapy appointment, or an evening free from care administration, protecting this time creates enough psychological and physical distance to recognize what structural changes are truly necessary.
Notice the Signs Before Care Becomes Impossible
For many individuals, recognizing caregiver burnout begins after a particularly rough day highlights how fragile their current routine has become. Rather than relying on rigid scoring checklists, experts suggest looking for persistent changes across multiple areas of life—specifically exhaustion that regular rest cannot shift, feelings of dread before routine care tasks, growing irritability or emotional detachment, forgotten steps in daily routines, missed work responsibilities, social isolation, or a total loss of personal interests outside of the caregiving role.
Because these signs can frequently overlap with clinical depression, anxiety disorders, sleep disturbances, medication side effects, or underlying physical illnesses, tracking the pattern and sharing it with a qualified medical professional is critical. Recognizing that the care arrangement itself may be unsafe is often the first step toward reclaiming functional stability.
Ultimately, navigating caregiver burnout requires stepping away from the belief that love must be proven by making one’s own capacity invisible. By systematically evaluating the actual care load, transferring critical tasks where possible, and seeking appropriate professional and community support, caregivers can begin to address the structural realities of their responsibilities without sacrificing their own health and well-being.



Leave a Reply