
For millions of women navigating the menopausal transition, nighttime rest does not simply feel lighter or shorter; it feels fundamentally altered. Menopause sleep problems typically show up at both ends of the night, making it noticeably harder both to fall asleep and to stay asleep. Longitudinal data from the landmark Study of Women’s Health Across the Nation (SWAN), which meticulously followed 3,045 women aged 42 to 52 at enrollment, demonstrated that the statistical odds of experiencing both types of sleep disruption steadily rise across the entire menopausal transition.
The frustrating hallmark of this phenomenon is its repetitive nature. The nights echo one another with a wearisome familiarity, often occurring when nothing else in a woman’s daily life, stress levels, or routines has changed. That precise combination—the repeating pattern unanchored to external stressors—is the classic tell, and it explains why generic sleep hygiene advice so frequently fails to provide relief.
For a significant number of women, the staying-asleep phase is the most disruptive, following a remarkably predictable and exhausting trajectory. A woman might fall asleep easily by 11:00 p.m., only to jolt awake at 2:40 a.m. feeling damp, kicking off the heavy covers before pulling them right back on as a chill sets in. She may drift off again, only to wake up once more at 4:15 a.m., finally resigning herself to get out of bed at 6:00 a.m. because professional responsibilities and daily life demand it.
By the time Thursday arrives, the cumulative deficit takes a heavy toll. Exhaustion manifests as a short temper with loved ones and the frustrating necessity of rereading the same work email four separate times just to comprehend its contents. Secondary analyses spanning ten years of data from the same SWAN cohort revealed that self-reported insomnia symptoms affected 31% of women in early perimenopause during their first year, climbing to 39% by year ten. Among women in late perimenopause, the prevalence started at 32% and rose steeply to 48%.
These figures represent self-reported symptoms occurring at least three times a week rather than clinically diagnosed chronic insomnia, and they naturally fluctuate across different stages and years. Nevertheless, experiencing them serves as a stark reminder that this struggle is shared, even if it feels profoundly isolating at 3:00 a.m. Perhaps most distinctively, women in this phase often develop a psychological dread of the bed itself—a novel and burdensome development that carries far more clinical weight than any over-the-counter supplement sitting on a bathroom shelf.
Why the Usual Natural Remedies Keep Failing You
Natural remedies for broken midlife sleep routinely fail because they are typically encountered as an unorganized list of options lacking clear mechanisms, prioritization, or proper grading of supporting evidence. Melatonin offers the clearest illustration of this disconnect. When researchers pooled data across four separate randomized trials involving menopausal women, the observed effect on overall sleep quality did not reach statistical significance. In scientific terms, this indicates uncertain efficacy rather than definitive disproof, a nuanced distinction that rarely makes it onto the label of a retail box.
Valerian root fares no better under scientific scrutiny. An umbrella review published in 2024 synthesized eight distinct systematic reviews evaluating valerian for sleep disturbances, ultimately judging the underlying evidence to be weak or inconclusive, with no demonstrable evidence of efficacy specifically for insomnia.
Faced with these options, a woman might try one remedy, give it an earnest two-week trial, feel no tangible benefit, and quietly conclude that the fault lies within her own biology. In reality, the problem is not personal failure. The issue stems from being handed a crowded retail shelf and told to guess, which represents a fundamentally flawed approach to treating menopause-related insomnia—a complex condition driven by at least three distinct underlying causes.
Menopause Sleep Problems Are a Wake-Up Pattern, Not One Problem
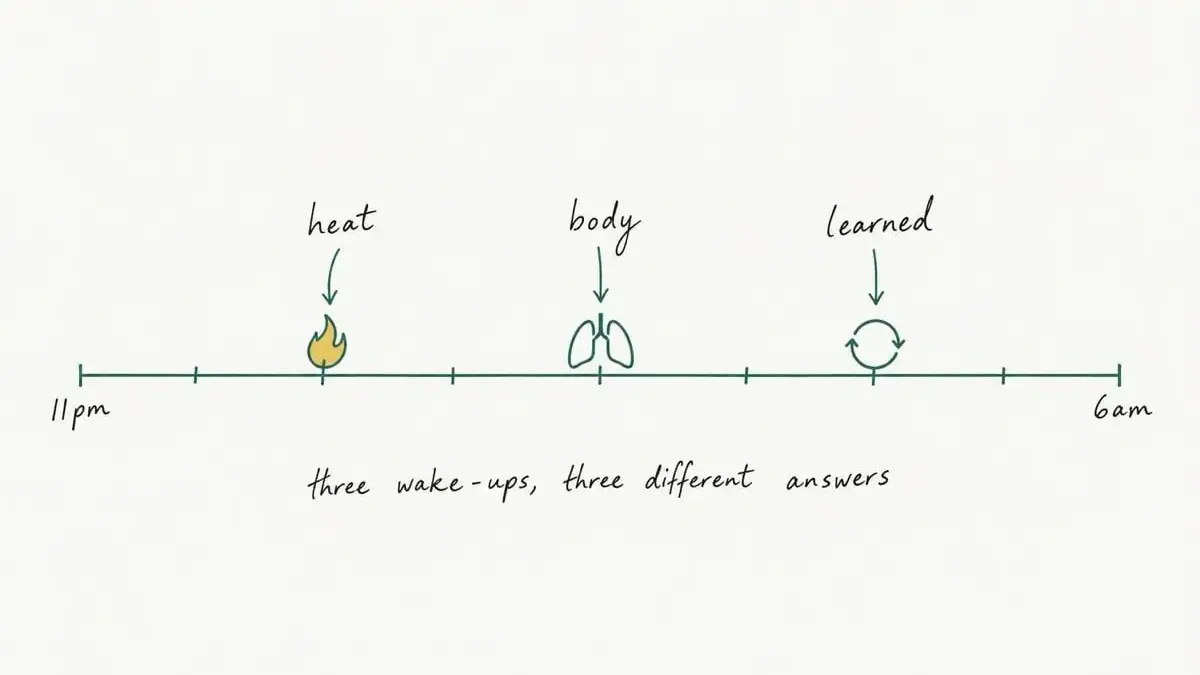
Menopause-related sleep disruptions cannot be treated as a single, uniform issue. Instead, they manifest as at least three distinct wake-up patterns wearing the disguise of a single symptom: heat-driven waking, body-driven waking stemming from physiological shifts like disordered breathing, and learned waking that persists long after the initial physiological triggers have faded. A remedy aimed at just one of these patterns will inevitably do little to alleviate the other two. Determining which specific pattern dominates a woman’s nights is what transforms a random list of tips into a coherent medical and behavioral decision.
Heat-driven waking is the phenomenon most commonly associated with menopause, and its physiological reality is well-documented. In an observational study of 168 midlife women monitored using actigraphy, 78% of objectively recorded nocturnal hot flashes coincided directly with an awakening episode. Furthermore, women were significantly more likely to be awake during the five minutes immediately following a hot flash than in the minutes leading up to it. While chronological concurrence does not definitively prove that every single awakening is initiated by a flash, the clinical link is difficult to dispute.
Body-driven waking, by contrast, is the pattern most frequently overlooked in primary care settings. Data from the Sleep in Midlife Women Study revealed that the adjusted apnea-hypopnea index—a standard measure of breathing events during sleep—was approximately 31% higher after the menopausal transition than before it. This metric tracks breathing disruptions rather than counting new clinical diagnoses of sleep apnea. What makes this finding clinically crucial is how the condition presents: women with obstructive sleep apnea often consult primary care physicians reporting symptoms of insomnia, persistent fatigue, and low mood rather than classic snoring, which remains a primary reason the condition frequently goes undiagnosed in female patients.
Learned waking explains why many women remain wide awake at 3:00 a.m. years after their hot flashes have completely subsided. Over time, the bed has transitioned into a stressful environment associated with lying awake performing mental arithmetic about the upcoming day. This is no longer a hormone-driven problem, yet it is precisely the pattern backed by the most robust, evidence-based non-pharmacological treatments available.
While sorting troublesome nights into these three categories serves as an organizational framework rather than a rigid clinical classification—and real-world weeks often feature a blend of all three—it remains exceptionally useful. Each group points directly toward a different, targeted next step.
Natural Remedies, Ranked by the Evidence Behind Them
When ranked strictly by the strength of scientific evidence supporting them, natural and non-pharmacological remedies for menopause sleep problems follow a clear hierarchy: cognitive behavioral therapy for insomnia (CBT-I) ranks first, regular physical exercise ranks second, and dietary supplements occupy a distant third.
In a randomized controlled trial involving 106 midlife women experiencing frequent hot flashes and insomnia, telephone-delivered CBT-I reduced insomnia severity scores by approximately 5.2 points more than a menopause-education control group at eight weeks, with these therapeutic gains successfully maintained at the 24-week follow-up. No dietary supplement possesses clinical evidence operating in that therapeutic range.

First: CBT-I, Which Is a Treatment, Not a Tip
CBT-I is a structured, short-term behavioral intervention typically lasting between four and eight sessions, delivered either by a trained clinician, a specialized therapist, or a guided digital platform. The treatment focuses squarely on the mechanical aspects of sleep: establishing a single, consistent wake time every day, restricting time spent in bed to closely match actual sleep duration, getting out of bed rather than lying awake frustrated, and dismantling the psychological thought loops that trigger nocturnal alertness.
Professional medical guidelines consistently point to CBT-I as the primary intervention of choice. The American College of Physicians recommends CBT-I as the initial treatment for all adults suffering from chronic insomnia, issuing a strong recommendation based on moderate-quality evidence, with medication reserved for shared decision-making if behavioral therapy alone proves insufficient. While that particular guideline applies broadly to adults with chronic insomnia rather than exclusively to menopausal populations, clinical trials specifically featuring midlife women with hot flashes and insomnia demonstrate matching therapeutic efficacy.
A vital distinction must be made regarding sleep hygiene. The American Academy of Sleep Medicine recommends the comprehensive, multicomponent version of CBT-I while explicitly advising against relying on basic sleep hygiene tips as a stand-alone treatment. Consequently, maintaining a tidy list of habits such as keeping a dark room, avoiding screens, and cutting off late caffeine intake is not the treatment itself; it merely establishes the baseline floor.
Second: Exercise, With an Honest Effect Size
Pooled individual-participant data across four clinical trials conducted by the MsFLASH research network revealed that regular physical exercise reduced Insomnia Severity Index scores by an average of 2.1 points relative to control groups, compared to the larger 5.2-point reduction achieved through CBT-I. A two-point improvement represents a real and modest therapeutic benefit—worth pursuing, but insufficient to carry the entire weight of managing severe midlife sleep disruption.
Third: Supplements, With Their Evidence Attached
The scientific literature surrounding common sleep supplements reveals a stark gap between commercial marketing and verifiable data. Supplements frequently interact with prescription medications and with one another, making professional consultation with a clinician or pharmacist an essential prerequisite before ingestion.
A Note on Cool-Bedroom Advice
Nearly every popular article addressing midlife sleep recommends lowering bedroom temperatures, yet researchers have found a distinct lack of controlled clinical evidence specifically showing that cooler room temperatures treat menopausal insomnia. Existing physiological studies in healthy adults indicate that warming the skin of the trunk and upper legs by less than one degree Celsius can shorten sleep-onset latency by approximately three minutes. However, that research neither explicitly supports nor refutes traditional menopausal cooling advice. The absence of robust clinical trials proving efficacy does not constitute evidence against using fans or breathable bedding, which remain valuable for comfort when managing night sweats, even if a household thermostat cannot resolve a psychological thought loop at 3:00 a.m.
What One Week of This Actually Looks Like
In practical execution, addressing midlife sleep disruptions methodically rather than haphazardly involves a straightforward observational approach. A woman selects a single, immovable wake-up time and maintains it every day of the week, including Saturday. Each morning, she records three simple observations: the time she woke up during the night, whether heat played a role, and whether any respiratory issues or daytime fatigue surfaced. Ceasing the constant addition of new remedies allows the daily log, rather than a supplement label, to clarify which specific wake-up pattern is disrupting her nights.
Consider two hypothetical readers illustrating contrasting scenarios. Tricia, aged 49 in early perimenopause, logs four nocturnal wakings over seven nights, three of which involved changing damp sheets and turning on a bedroom fan, with no reported breathing issues. Her pattern is clearly heat-driven. Her management strategy avoids purchasing a flurry of products; instead, she establishes a fixed 6:15 a.m. wake time, incorporates daily walks, utilizes breathable bedding, and notes the frequency of her hot flashes for her next clinical appointment.
Marlene, aged 54 and two years past her final menstrual period, experiences minimal hot flashes but continues to wake consistently at 3:10 a.m., spending up to 90 minutes composing mental to-do lists. Her log reveals no heat involvement but highlights a learned behavioral pattern. Furthermore, her breathing column notes occasional snoring mentioned by her spouse and daytime fatigue leading to early evening somnolence in front of the television. Her path forward involves two distinct steps: discussing CBT-I with her physician to address the learned nighttime wakefulness, and raising her snoring and daytime sleepiness during the same consultation. In the interim, she leaves her bed after 20 minutes of wakefulness to avoid reinforcing the association between bed and mental activity.
Both women maintain their logs for a full week before altering any routines, avoiding the common pitfall of simultaneously adopting magnesium supplements, blackout curtains, specialized pillows, and sleep tracking applications, which obscures the source of any potential relief.
When This Needs a Clinician, Not a Remedy
Certain nighttime symptoms transcend simple self-care adjustments. Loud snoring, breathing that repeatedly pauses and starts, gasping or choking sounds, and persistent daytime exhaustion are recognized as primary indicators of obstructive sleep apnea by healthcare authorities like the UK’s National Health Service, which advises seeking formal medical evaluation rather than experimenting with retail supplements. Similarly, sleep difficulties persisting at least three times a week for three months or longer meet the established diagnostic frequency and duration threshold for chronic insomnia defined by the American Academy of Sleep Medicine.
Attributing these symptoms solely to the assumption that it is "just menopause" remains the most common clinical pitfall, frequently delaying proper diagnosis by a year or more. Because sleep-disordered breathing in women often presents atypically through insomnia, fatigue, and low mood rather than classic snoring, professional evaluation is essential.
Hormone therapy warrants careful consideration during these medical consultations. According to the 2002 position statement from The North American Menopause Society, hormone therapy remains the most effective FDA-approved treatment for moderate to severe hot flashes and night sweats, yielding secondary improvements in sleep quality when disturbances are directly tied to vasomotor symptoms. It is not prescribed as a stand-alone treatment for primary insomnia, and its suitability requires an individualized benefit-risk assessment conducted alongside a qualified clinician.
Start With One Night, Not Eight Changes
Selecting a consistent wake-up time before purchasing any remedy establishes a solid foundation. Placing a simple notepad by the bed to record the hour of waking, the presence of heat, and any observations regarding breathing or daytime fatigue for seven consecutive nights provides a practical diagnostic baseline. Maintaining one fixed wake time without adding external interventions transforms a frustrating cycle of guesswork into a focused, evidence-based discussion with a healthcare provider, offering a clearer path toward restorative rest.



Leave a Reply