
For millions of women navigating the menopausal transition, nighttime disruptions do not arrive as a gentle invitation to rest. Instead, they manifest as a frustrating double blow at both ends of the night: it becomes increasingly difficult to fall asleep at the onset, and nearly impossible to stay asleep through the early morning hours. Data from the landmark Study of Women’s Health Across the Nation (SWAN), which meticulously followed 3,045 women enrolled between the ages of 42 and 52, indicates that the statistical odds of experiencing both types of sleep trouble rise steadily across the entire menopausal transition. The nights repeat in an exhausting loop. Nothing else in your life has fundamentally changed, yet your body refuses to cooperate. That specific combination is the ultimate tell, and it explains precisely why generic, one-size-fits-all sleep advice routinely bounces off midlife women without offering any genuine relief.
For a vast number of women, the staying-asleep half of the equation is the loudest and most disruptive, often following a painfully familiar shape. Sleep arrives by eleven without much resistance, only to be violently shattered at 2:40 a.m. You wake up damp, kicking the covers off in a sudden wave of heat, only to pull them back up minutes later as chills set in. Sleep claims you briefly again, only for you to jolt awake at 4:15 a.m. Eventually, you rise at six anyway, because professional obligations and daily responsibilities do not care how many hours of restorative rest you actually managed to capture.
By Thursday, the cumulative toll becomes unmistakable. You find yourself short with the people you love the most and staring blankly at your computer screen, rereading the exact same work email four separate times. A secondary analysis examining ten years of data from that same SWAN cohort revealed a sobering trajectory: insomnia symptoms were reported by 31 percent of women in early perimenopause during their first year, climbing steadily to 39 percent by year ten. Among women in late perimenopause, the prevalence started at 32 percent and surged upward to 48 percent. It is crucial to note that these figures reflect self-reported symptoms occurring at least three times a week rather than formal, clinical insomnia diagnoses, and they fluctuate depending on the specific menopausal stage and year. Nevertheless, these numbers confirm a vital truth: you are not the isolated outlier you desperately feel like you are at 3:00 a.m.
Compounding the physical exhaustion is a psychological shift that catches many women off guard. You have started to genuinely dread the bed itself. That sense of dread is entirely new, and clinically speaking, it matters far more than any trendy supplement sitting on your kitchen counter.
Why the Usual Natural Remedies Keep Failing You
Natural remedies for broken midlife sleep almost invariably fail because they arrive as an unorganized list of half a dozen options devoid of context, underlying mechanisms, or any grading of the scientific evidence supporting them. Melatonin serves as the clearest example of this phenomenon. When pooled across four randomized clinical trials specifically involving menopausal women, the overall effect on sleep quality was found not to be statistically significant. In scientific terms, that means the evidence is uncertain rather than outright disproven, which creates a wide gulf between clinical reality and what the marketing label on the box loudly suggests.
Herbal alternatives like valerian root fare no better under scientific scrutiny. An umbrella review published in 2024 synthesized eight systematic reviews examining valerian for sleep disturbances and ultimately judged the available evidence to be weak or inconclusive, finding no verifiable evidence of efficacy for treating insomnia. Consequently, a woman desperate for relief will try one remedy, give it an honest two-week trial, feel absolutely no difference, and quietly conclude that the fundamental problem lies within her own discipline or body. It does not. Instead, she was simply handed a retail shelf and told to guess—a profoundly ineffective way to treat menopause insomnia, which is a complex condition driven by at least three entirely separate physiological causes.
Menopause Sleep Problems Are a Wake-Up Pattern, Not One Problem
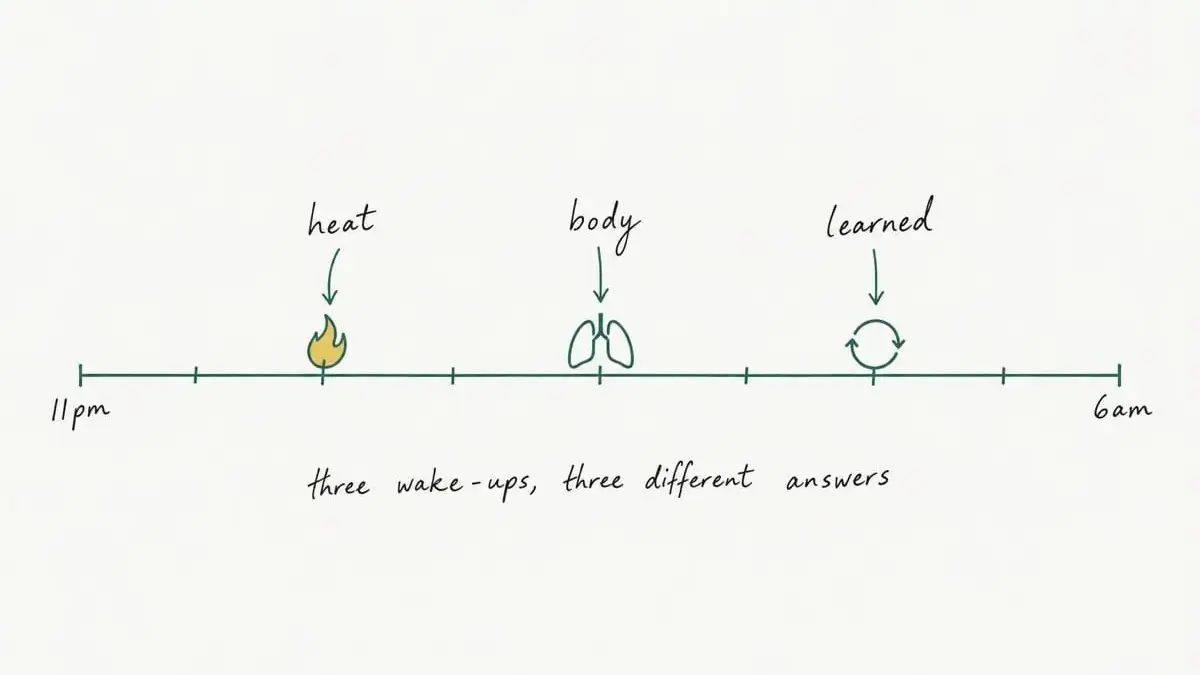
Menopause-related sleep disturbances cannot be treated as a monolithic issue. They are, in reality, at least three distinct wake-up patterns wearing the exact same frustrating symptom: heat-driven waking, body-driven waking stemming from issues such as disordered breathing, and learned waking that stubbornly outlives the hot flashes themselves. A remedy specifically aimed at one of these patterns will naturally do very little to resolve the other two. Determining which specific pattern dominates your nights is what transforms an overwhelming, random list of remedies into a coherent clinical decision.
Heat-driven waking is the phenomenon everyone instantly pictures, and its physiological reality is well-documented. In a study of 168 midlife women monitored continuously with actigraphy, 78 percent of objectively recorded nocturnal hot flashes coincided directly with an actual waking episode. Furthermore, these women were significantly more likely to be awake in the five minutes immediately following a flash than in the minutes leading up to it. While mere concurrence does not mathematically prove that every single awakening starts with a thermal surge, the clinical link is exceedingly difficult to dismiss.
Body-driven waking represents the pattern that is most frequently missed by primary care providers and patients alike. Data from the Sleep in Midlife Women Study revealed that the adjusted apnea-hypopnea index was roughly 31 percent higher after the menopausal transition than it was before it. This metric measures measurable breathing events during sleep rather than counting formal new apnea diagnoses. What makes this finding critical to understand is how the condition actually presents in real life: women suffering from obstructive sleep apnea frequently visit primary care clinics reporting complaints of stubborn insomnia, persistent fatigue, and low mood rather than classic snoring, which remains a primary reason the condition is so frequently overlooked or misdiagnosed in female patients.
Learned waking explains why a substantial number of women remain wide awake at 3:00 a.m. years after their hot flashes have completely faded into memory. Over time, the bed unconsciously transforms into a stressful location where you lie awake performing mental arithmetic about the demanding day ahead. At this stage, the disruption is no longer primarily driven by fluctuating hormones, yet this specific pattern responds remarkably well to targeted, evidence-backed behavioral treatments. While sorting sleepless nights into these distinct categories serves as an organizational framework rather than a rigid clinical classification, it remains intensely useful because each distinct group points directly toward a different, more effective next step.
Natural Remedies, Ranked by the Evidence Behind Them
When evaluated strictly by the strength of the clinical evidence supporting them, natural and non-pharmacological remedies for menopause sleep problems fall into a clear hierarchy: cognitive behavioral therapy for insomnia ranks first, regular exercise claims the second spot, and dietary supplements sit a distant third. In a randomized controlled trial involving 106 midlife women suffering from frequent hot flashes and co-occurring insomnia, telephone-delivered cognitive behavioral therapy for insomnia improved insomnia severity scores by an impressive 5.2 points more than a menopause-education control group at the eight-week mark, and those hard-won clinical gains held firm at the 24-week follow-up evaluation. No over-the-counter supplement possesses clinical evidence that even approaches that range of effectiveness.
The first tier belongs firmly to cognitive behavioral therapy for insomnia, which functions as a structured clinical treatment rather than a collection of casual wellness tips. Typically delivered across four to eight sessions by a trained clinician, therapist, or guided digital program, CBT-I targets the core behavioral and cognitive mechanics of sleep. It establishes a single, unwavering wake time that the patient maintains every day of the week, restricts time spent lying in bed to match the actual amount of sleep the body is currently generating, instructs patients to get out of bed rather than lying awake tossing and turning, and systematically dismantles the frantic thought loops that plague the 3:00 a.m. hours.
Professional medical guidelines strongly endorse this approach. The American College of Physicians recommends cognitive behavioral therapy for insomnia as the initial, primary treatment for all adult patients struggling with chronic insomnia, issuing a strong recommendation based on moderate-quality evidence, while positioning medication as a secondary, shared decision if behavioral therapy alone proves insufficient. While that particular guideline applies broadly to adults with chronic insomnia rather than exclusively to menopausal women, the aforementioned clinical trial bridges that gap directly by focusing entirely on midlife women experiencing hot flashes and sleep disruption.

A vital caveat emphasized by the American Academy of Sleep Medicine is that patients should pursue the comprehensive, multicomponent version of CBT-I while actively avoiding sleep hygiene education when used merely as a stand-alone treatment. Consequently, the familiar, tidy checklist of maintaining a dark room, avoiding screens before bed, and cutting off caffeine late in the afternoon is not an adequate treatment on its own; rather, it merely represents the baseline floor of healthy sleep habits.
Exercise claims the second tier in the evidentiary hierarchy, offering an honest and measurable effect size. Pooled individual-participant data compiled across four separate MsFLASH clinical trials demonstrated that regular exercise successfully reduced Insomnia Severity Index scores by an average of 2.1 points relative to control groups. While a two-point reduction is a modest improvement, it is nonetheless a genuine and worthwhile physiological benefit—even if it is not robust enough to carry the entire therapeutic load on its own.
Supplements occupy the third and final tier, accompanied closely by the specific scientific data detailing their actual performance. Because supplements frequently interact negatively with prescription medications and with each other, healthcare providers invariably advise patients to run any botanical product past a qualified physician or pharmacist before beginning use. Meanwhile, popular advice regarding keeping the bedroom exceptionally cool lacks robust controlled clinical trials demonstrating that ambient room temperature directly treats menopausal insomnia. While cooling the environment certainly offers valuable comfort when dealing with oppressive night sweats, keeping a fan running or choosing breathable bedding should be viewed as practical comfort measures rather than curative treatments for a disrupted sleep architecture.
What One Week of This Actually Looks Like
In practical terms, adopting an evidence-based approach to midlife sleep disruption looks remarkably unglamorous. Rather than overhauling your entire life overnight, you begin by selecting a single, consistent wake time and holding it rigidly without exception, including on Saturdays. Each morning, you record three simple details on a bedside notepad: the exact hour you woke up, whether a hot flash or heat was involved, and whether any breathing-related issues or profound daytime fatigue surfaced. You deliberately stop purchasing new supplements or downloading unproven sleep apps. By the fifth day, this straightforward daily log—rather than a vague supplement marketing label—reveals precisely which wake-up pattern is dominating your nights.
Consider two hypothetical readers illustrating how this decision-making process operates in the real world. Tricia, a 49-year-old woman in early perimenopause, maintains a sleep log that documents four disruptive wakings over the course of seven nights, three of which required changing damp sheets and turning on a bedside fan, with zero entries in the breathing column. Her pattern is clearly heat-driven. Her action plan avoids an overwhelming list of eight sweeping lifestyle modifications; instead, she establishes a fixed wake time of 6:15 a.m., incorporates a daily walk, switches to lightweight, breathable bedding, and compiles a concise note for her upcoming physician appointment detailing the exact frequency of her night sweats. She purchases no new products. Furthermore, her structured log transforms a vague, distressing mental complaint of "I never sleep anymore" into precise clinical data: four nights out of seven, featuring three distinct night sweat episodes, persisting consistently for eleven weeks.
Marlene, aged 54 and two years past her final menstrual period, experiences a different reality. Her hot flashes have largely subsided, yet she continues to wake predictably at 3:10 a.m. Her sleep log reveals an absence of thermal events accompanied by a persistent behavioral habit of lying awake in bed for 90 minutes composing tomorrow’s extensive to-do list. However, her breathing column is not entirely blank; her husband has casually mentioned hearing her snore on multiple occasions, and she frequently catches herself falling fast asleep in front of the television by eight o’clock in the evening. Consequently, her log generates two distinct clinical priorities: discussing cognitive behavioral therapy for insomnia with her doctor to address the learned wake-up pattern, and explicitly raising the issues of nighttime snoring and severe daytime sleepiness during that same medical appointment rather than dismissing them as ordinary fatigue. In the interim, she resolves to get out of bed whenever she finds herself awake for more than 20 minutes, refusing to train her brain to associate the mattress with anxious nocturnal rumination.
Both women successfully maintain their sleep logs for a full week before implementing any external changes, effectively avoiding the classic trap of launching magnesium supplements, blackout curtains, expensive pillows, and sleep tracking applications all in the same week and learning nothing actionable from the experiment.
When This Needs a Clinician, Not a Remedy
Certain nocturnal disruptions clearly transcend the scope of casual home remedies. Symptoms such as loud, persistent snoring, breathing that repeatedly stops and starts during sleep, sudden gasping or choking noises, and a pervasive, inescapable exhaustion throughout the day are recognized indicators of underlying sleep-disordered breathing. Major health organizations consistently advise individuals experiencing these symptoms to consult a qualified physician rather than fruitlessly navigating retail supplement aisles. Similarly, sleep disturbances that persist at or above a frequency of three nights a week for three months or longer meet the established clinical threshold for chronic insomnia defined by the American Academy of Sleep Medicine.
Medical professionals frequently caution that dismissing these symptoms with the assumption that "it’s just menopause" is the single most common diagnostic pitfall, often costing patients a year or more of unnecessary suffering. Because sleep-disordered breathing in women frequently presents with atypical symptoms like insomnia, fatigue, and low mood rather than classic, disruptive snoring, professional evaluation is essential.
For many women, discussing hormone therapy during this medical consultation represents a productive avenue to explore. Position statements issued by leading North American menopause organizations identify hormone therapy as the single most effective systemic treatment for moderate to severe hot flashes and night sweats, noting subsequent improvements in sleep quality when the underlying nocturnal disturbances are directly tied to those vasomotor symptoms. Hormone therapy is not intended to function as a stand-alone treatment for primary insomnia, and determining its appropriateness requires a personalized benefit-risk assessment conducted alongside a qualified healthcare provider.
Start With One Night, Not Eight Changes
For women exhausted by years of broken rest, the path forward begins with a remarkably simple, deliberate choice: select your consistent morning wake time before you ever think about purchasing a remedy. Place a blank sheet of paper and a pen on your bedside table tonight, dividing it into three simple columns to track the hour you wake, whether thermal heat played a role, and any observations regarding your breathing or daytime fatigue. Maintain that simple routine for seven consecutive nights while holding a single, unwavering wake time and changing nothing else in your daily habits.
That modest log functions as the most reliable, cost-effective diagnostic tool available, instantly transforming the overwhelming world of menopause sleep remedies from a shelf of desperate guesses into a short, manageable list of targeted solutions that deserve an honest trial. Above all, it provides your healthcare provider with concrete, actionable data rather than a generalized expression of exhaustion, opening the door to genuine relief.



Leave a Reply